Tariq Drabu's Posts (351)

Sort by

thumb-sucking-girl-dr.-dunne-a-childs-best-smile-girl-sucking-thumb.jpg

Parents often hear that thumb-sucking will "ruin" a child's teeth, and just as often hear that kids grow out of it and it doesn't matter. The truth sits in between. Many common childhood habits are perfectly normal at one age and potentially harmful at another. This article explains how habits like thumb-sucking, pacifier use, tongue thrusting, and mouth breathing affect developing teeth and jaws, when to be concerned, and how dental professionals help.

Why Habits Affect the Mouth

A child's jaws and teeth are shaped not only by genetics but by the forces placed on them every day. The tongue, lips, and cheeks create a balance of pressure that guides where teeth erupt and how the jaws grow. When a habit repeatedly changes those forces over months or years, the teeth and bones gradually adapt to the new pressure.

The three factors that matter most are duration (how many hours a day), frequency (how often), and intensity (how forcefully). A child who sucks a thumb gently while falling asleep is very different from one who sucks vigorously for hours each day.

Thumb and Finger Sucking

Sucking is a natural reflex, and it comforts babies and toddlers. Most children stop on their own between ages two and four. Problems are more likely when the habit continues as the permanent front teeth start to come in, usually around age six.

Prolonged, intense sucking can lead to:

  • Anterior open bite, where the front teeth don't meet when the back teeth are closed
  • Protruding upper front teeth, which are more prone to injury
  • A narrow upper jaw, which can cause a posterior crossbite
  • Changes in how the tongue rests and moves during swallowing and speech

Pacifiers

Pacifiers can cause similar changes, although the habit is often easier to stop because the pacifier can be taken away. Many pediatric dental professionals encourage weaning well before the permanent teeth erupt, and ideally in the toddler years. Never dip a pacifier in honey or sugar, which dramatically increases cavity risk.

Tongue Thrust

Normally, the tongue rests against the roof of the mouth and pushes upward and back during swallowing. With a tongue thrust, the tongue pushes forward against or between the front teeth. That repeated pressure can keep an open bite from closing and can push teeth forward. Tongue thrust often goes hand in hand with a lingering sucking habit or with mouth breathing, and it sometimes needs help from a speech-language pathologist or myofunctional therapist.

Mouth Breathing

This habit is easy to overlook but can have significant effects. Children who breathe mostly through the mouth often do so because of enlarged tonsils or adenoids, allergies, or nasal blockage. When the mouth stays open, the tongue drops away from the palate, removing a force that helps the upper jaw widen.

Over time, chronic mouth breathing has been associated with:

  • A narrow, high-arched palate
  • Crowded teeth and crossbites
  • A longer lower face
  • Dry mouth, which raises cavity and gum inflammation risk
  • Snoring and disrupted sleep, which can affect behavior, attention, and growth

Signs to watch for include snoring, lips apart at rest, dark circles under the eyes, frequent congestion, restless sleep, and daytime fatigue. Because the cause is often in the airway, a dentist may recommend an evaluation by a pediatrician or an ear, nose, and throat specialist.

Why Both Specialists Matter

Habit-related problems sit at the intersection of two dental specialties. A pediatric dentist sees a child every six months from infancy and is often the first to notice early changes in the bite, a habit that isn't fading, or signs of mouth breathing. An orthodontist evaluates how the jaws are growing and corrects the effects once they develop.

The American Association of Orthodontists recommends an orthodontic evaluation around age seven. For habit-related issues, that timing is especially useful, because many problems caused by habits are easier to correct while a child is still growing. A practice with both an orthodontist & pediatric dentist on the same team can monitor a habit, step in when needed, and coordinate care without passing the family between offices.

How Habits Are Addressed

Positive reinforcement first. For young children, praise, sticker charts, and small rewards for habit-free days are often more effective than scolding. Many children suck their thumbs when tired, bored, or anxious, so addressing the trigger helps.

Reminders. Bandages on the thumb, special gloves at night, or bitter-tasting nail coatings recommended by a dentist can serve as gentle reminders for older children who want to stop.

Habit appliances. If a child wants to stop but can't, a dentist or orthodontist may place a small appliance behind the upper front teeth that makes sucking less satisfying and reminds the tongue where to rest.

Palatal expansion. When a habit or mouth breathing has narrowed the upper jaw, an expander can widen it while the growth seam in the palate is still flexible, typically before the early teen years. This can correct a crossbite and create room for crowded teeth.

Myofunctional therapy. Exercises that retrain the tongue and lip muscles can support orthodontic treatment for tongue thrust and open bites.

Airway coordination. If enlarged tonsils or allergies are causing mouth breathing, treating the underlying cause may be the most important step.

What Parents Can Do

  • Don't panic about sucking habits in babies and toddlers. They're normal.
  • Begin gently discouraging the habit as a child approaches preschool age.
  • Watch for mouth breathing and snoring at any age, and mention them to your child's dentist and pediatrician.
  • Keep up with six-month dental visits so changes are spotted early.
  • Schedule an orthodontic evaluation around age seven, even if the teeth look fine.

The Bottom Line

Most childhood habits are harmless when they fade on time. When they persist, especially past the point when permanent teeth arrive, they can reshape the bite and even the jaws. Early attention from a pediatric dentist, timely orthodontic evaluation, and a supportive approach at home can prevent small problems from becoming bigger ones and help children grow into healthy, well-aligned smiles.


Read more…

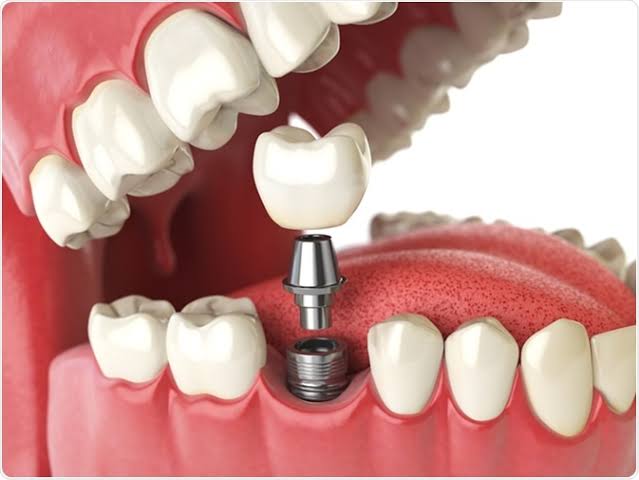
For decades, a "dental implant" meant a titanium post. Titanium still accounts for the vast majority of implants placed today, and it has an excellent track record. But a growing number of patients ask about zirconia, a ceramic material that offers a metal-free alternative. Both can replace missing teeth successfully, and each has real advantages and limitations. This article compares the two so you can have an informed conversation with your dentist.

A Quick Primer on Implants

A dental implant replaces the root of a missing tooth. It's placed in the jawbone, where bone gradually bonds to its surface. Once healed, it supports a crown, a bridge, or a full-arch set of teeth. Implants help preserve the jawbone, don't rely on neighboring teeth for support, and can last for many years with good care.

The material the implant is made from affects how it bonds with bone, how it looks, how it handles stress, and how the final tooth is attached.

Titanium Implants

Titanium implants have been used since the 1960s and have been studied extensively. They are typically made from commercially pure titanium or titanium alloys.

Strengths:

  • Long-term research. Decades of clinical data show high success rates over ten years and beyond.
  • Strength and flexibility. Titanium tolerates chewing forces well and is very resistant to fracture.
  • Two-piece design. Most titanium implants have a separate abutment, the connector between implant and crown. That gives the dentist flexibility to adjust angles and replace components if needed.
  • Wide range of options. Nearly every size, shape, and restorative system is available.

Limitations:

  • Gray show-through. In patients with thin gums, especially in the front of the mouth, a gray shadow can sometimes appear at the gumline, or become visible if the gums recede.
  • Metal sensitivity. True titanium allergy appears to be rare, but some patients have documented sensitivities or simply prefer to avoid metal in their bodies.
  • Corrosion particles. Researchers continue to study the small particles and ions that can be released from titanium surfaces over time and their possible role in inflammation around implants.

Zirconia Implants

Zirconia is a white, tooth-colored ceramic, specifically yttria-stabilized zirconium dioxide. It has been used in dentistry for crowns and bridges for years and has been used for implants more recently.

Strengths:

  • Metal-free. A natural fit for patients seeking a biocompatible, non-metal option, as offered by practices focused on Biodental Holistic Dentistry.
  • Aesthetics. The white color blends with natural teeth and won't cause a gray shadow at the gums.
  • Soft-tissue response. Several studies suggest that zirconia may accumulate less plaque than titanium and that gums tend to respond well to it.
  • No galvanic reaction. Because it isn't metal, zirconia doesn't conduct electricity or interact with other metals in the mouth.

Limitations:

  • Less long-term data. Short- and medium-term results are encouraging, but the research base is much smaller than for titanium.
  • More brittle. Ceramic is strong under compression but less forgiving under bending forces. Fracture is uncommon with modern designs but more of a concern than with titanium, particularly in patients who grind heavily.
  • Design limitations. Many zirconia implants are one-piece, meaning the implant and abutment are a single unit. That limits adjustments and can make healing more sensitive to forces during the early months. Two-piece zirconia systems are available and becoming more common.
  • Fewer options. Fewer sizes and restorative components exist, and fewer clinicians are trained in placing them.
  • Cost. Zirconia implants often cost more.

Side-by-Side Comparison

Factor

Titanium

Zirconia

Color

Gray metal

White, tooth-colored

Research history

50+ years

Shorter, growing

Fracture resistance

Very high

High, but more brittle

Design

Mostly two-piece

One-piece and two-piece

Metal-free

No

Yes

Gum aesthetics with thin tissue

Possible gray show-through

No gray show-through

Availability

Nearly universal

More limited

Typical cost

Lower

Higher


Who Might Prefer Zirconia?

Zirconia can be a good choice for patients who:

  • Have a documented metal allergy or sensitivity
  • Strongly prefer a metal-free mouth for personal or holistic reasons
  • Have thin gum tissue in a highly visible area
  • Are replacing front teeth where aesthetics are critical

Titanium may be the better choice for patients who:

  • Grind or clench heavily
  • Need implants placed at angles or require complex full-arch restorations
  • Need bone grafting with immediate implant placement in challenging sites
  • Want the option with the longest track record

The Role of Planning and Technology

Regardless of material, implant success depends on careful planning. 3D cone-beam imaging shows bone volume and the location of nerves and sinuses. Digital scans and guided surgery, including robotic-assisted placement at some practices, help position implants with high precision. Healthy gums, adequate bone, good blood sugar control, and not smoking all improve outcomes.

Questions to Ask Your Dentist

  • Which material do you recommend for my situation, and why?
  • How many zirconia implants have you placed, and what has your success rate been?
  • Is the zirconia implant one-piece or two-piece?
  • Will I need bone grafting first?
  • What are the full costs, including the crown?
  • How will we protect the implant if I grind my teeth?

Caring for Any Implant

Implants can't get cavities, but the gums and bone around them can become inflamed, a condition called peri-implantitis. Daily brushing, cleaning between teeth with floss or interdental brushes, regular professional cleanings, and a night guard if you grind all help protect your investment.

The Bottom Line

Titanium remains the proven standard, with decades of evidence behind it. Zirconia offers a metal-free, highly aesthetic alternative that suits many patients well, with growing research support. The best choice depends on your bite, your bone, your aesthetic goals, and your personal priorities. A thorough evaluation and an honest conversation about the trade-offs will help you choose the implant that fits you.

Read more…

what-are-the-3-types-of-dental-implants.jpg

Dental implants are widely considered the most natural-feeling way to replace missing teeth. But many people who come in for an implant consultation hear an unexpected word: grafting. It turns out that the bone under a missing tooth doesn't just sit there waiting. It changes, often dramatically, and that affects whether an implant can be placed. This article explains why bone matters, how grafts and sinus lifts work, and what patients should know before starting treatment.

Why Bone Is the Foundation of an Implant

An implant is a small post, usually titanium, that replaces a tooth's root. After it's placed, the surrounding bone grows onto its surface in a process called osseointegration. Once that bond forms, the implant can support a crown, bridge, or denture under full chewing forces.

For that to happen, the implant needs to be surrounded by enough healthy bone, typically with at least a millimeter or two of bone on every side. Too little height and the implant might reach a nerve or the sinus. Too little width and the implant can be exposed through the side of the ridge.

What Happens to Bone After a Tooth Is Lost

The jawbone around a tooth exists largely to support that tooth. When the tooth is removed, the body no longer gets the stimulation from chewing, and the bone begins to remodel and shrink.

Research has shown that the ridge can lose a substantial share of its width within the first year after an extraction, with most of that change happening in the first few months. Over years, the loss continues. That's why people who have worn dentures for a long time often notice their dentures getting looser and their lower face looking shorter.

Other causes of bone loss include:

  • Advanced gum disease
  • Infections or cysts
  • Trauma to the jaw
  • Long-term denture wear
  • Developmental conditions

Types of Bone Grafts

A bone graft adds material to the jaw to rebuild lost volume. Over time, the body replaces or incorporates that material with its own bone. Grafts come from several sources:

Autografts use the patient's own bone, often taken from another area of the jaw. They contain living cells and are considered the gold standard for regeneration, but they require a second surgical site.

Allografts come from human donor bone that has been processed and sterilized by a tissue bank.

Xenografts are derived from animal sources, most often bovine bone, and act as a long-lasting scaffold.

Alloplasts are synthetic materials such as calcium phosphate compounds.

Surgeons often combine materials and cover the graft with a membrane that keeps soft tissue out while bone forms underneath. Some practices also use growth factors or platelet concentrates prepared from the patient's own blood to support healing.

Common Grafting Procedures

Socket preservation. Graft material is placed immediately after an extraction to limit the shrinkage that would otherwise occur. It's one of the simplest ways to protect the option of an implant later.

Ridge augmentation. When the ridge is too thin or short, bone is added to rebuild its width or height before or during implant placement.

Block grafts. For larger defects, a solid piece of bone is secured to the jaw with small screws.

Guided bone regeneration. Particulate graft material and a barrier membrane are used to grow bone in a specific area.

The Sinus Lift

In the upper back jaw, the maxillary sinus sits directly above the roots of the premolars and molars. After those teeth are lost, two things tend to happen: the bone shrinks from below, and the sinus expands downward. The result can be only a few millimeters of bone, far too little for an implant.

A sinus lift, or sinus augmentation, solves this by gently raising the thin membrane that lines the floor of the sinus and placing graft material in the space created. There are two main approaches:

  • Lateral window technique. A small opening is made in the side wall of the sinus to access the membrane. This is used when a lot of added height is needed.
  • Crestal approach. The membrane is lifted through the same site where the implant will go. This is less invasive and used when only a modest increase is needed.

Recovery usually involves some swelling and congestion. Patients are asked to avoid blowing their nose forcefully, sneezing with the mouth closed, and air travel for a short time.

Timing: Staged vs. Simultaneous

Sometimes the graft and the implant are placed in the same appointment. In other cases, the graft is allowed to heal for several months before the implant goes in. Larger grafts and sinus lifts that add a lot of height are more likely to be staged. Healing times commonly range from four to nine months, depending on the size of the graft and the materials used.

Why a Specialist's Experience Matters

Grafting and sinus lifts are technique-sensitive. Planning requires 3D cone-beam imaging to measure bone height, width, density, and the position of nerves and sinuses. Complications such as membrane tears or graft failure are uncommon in experienced hands but more likely without extensive training. A dental implant specialist who performs grafting routinely can often turn a "you're not a candidate" into a workable plan, and can explain realistic timelines and outcomes.

When evaluating a provider, ask:

  • How many grafts and sinus lifts do you perform each year?
  • Will you take a 3D scan before planning?
  • What graft materials do you use, and why?
  • Will my graft and implant be placed together or in stages?
  • Who designs and makes the final teeth, and is the lab in-house?

Protecting Your Options

If you're facing an extraction and think you might want an implant later, ask about socket preservation at the time the tooth is removed. It's much easier to preserve bone than to rebuild it. And if you've already lost teeth, getting evaluated sooner rather than later limits how much additional bone is lost.

The Bottom Line

Bone loss after tooth loss is normal, but it doesn't have to rule out implants. Bone grafting and sinus lifts are well-established procedures that rebuild the foundation an implant needs. With careful 3D planning and an experienced surgeon, most patients who were once told they didn't have enough bone can still enjoy stable, natural-feeling implant teeth.

Read more…

how-quickly-do-teeth-move-with-invisalign.jpeg

Clear aligners have gone from a niche option to one of the most requested orthodontic treatments for adults. Their appeal is obvious: nearly invisible trays, no brackets or wires, and the freedom to take them out for meals. But aligners are a medical treatment, not a cosmetic accessory, and they work best when patients understand how they function and what they require. This article explains the science behind aligner treatment, what the process involves, and how to tell whether they're right for you.

How Teeth Move

Teeth aren't fixed rigidly in the jaw. Each root is held in its socket by the periodontal ligament, a thin layer of fibers that acts like a shock absorber. When steady, gentle pressure is applied to a tooth, the bone on the pressure side slowly breaks down and new bone forms on the opposite side. The tooth moves a fraction of a millimeter at a time.

Braces create that pressure through brackets and wires. Clear aligners do it through a series of custom plastic trays, each shaped slightly differently from the one before. When you snap in a new tray, it doesn't quite match your teeth, and that small mismatch produces the force that moves them.

From Scan to Trays: The Treatment Process

  1. Digital scan and records. Instead of messy impressions, most practices use an intraoral scanner to create a detailed 3D model of your teeth. Photos and X-rays check the health of the roots and bone.
  2. Treatment planning. Software maps out the movement of each tooth from start to finish. The dentist or orthodontist reviews and adjusts the plan, deciding how far each tooth should move per stage and in what order. This clinical judgment is the most important part of the process.
  3. Attachments. Small tooth-colored bumps may be bonded to certain teeth. They give the aligners something to grip, allowing more complex movements like rotations and tipping.
  4. Wearing the trays. Patients typically switch to a new set every one to two weeks. Check-ups every six to ten weeks confirm that teeth are tracking as planned.
  5. Refinements. It's common to need an additional series of aligners near the end to fine-tune the result. This is a normal part of treatment, not a sign that something went wrong.
  6. Retainers. Once teeth reach their final positions, retainers keep them there.

The 20-to-22-Hour Rule

The single biggest factor in aligner success is wear time. Trays need to be in the mouth 20 to 22 hours a day, which means they come out only for eating, drinking anything other than water, and brushing.

Why is it so strict? Teeth begin to drift back as soon as the pressure is removed. A tray worn only 16 hours a day spends a third of each day letting teeth relax, which slows progress, causes trays to fit poorly, and can lead to extra refinements. Patients who are consistent usually finish on schedule.

Helpful habits include:

  • Keeping the case with you at all times
  • Brushing or at least rinsing before putting trays back in
  • Limiting grazing and sipping sweet drinks throughout the day
  • Setting phone reminders for the first few weeks

Who Is a Good Candidate?

Modern clear aligners work well for many common problems:

  • Mild to moderate crowding
  • Gaps between teeth
  • Some overbites, underbites, and crossbites
  • Relapse after earlier braces treatment
  • Straightening teeth before crowns, veneers, or implants

They may be less suitable for severe crowding, large vertical movements, significant skeletal bite problems, or patients who aren't able to wear them consistently. In those cases, braces may produce a more predictable result.

Before any tooth movement, the gums and teeth need to be healthy. Untreated cavities and gum disease should be addressed first.

Brand Names and What Really Matters

Invisalign is the best-known aligner brand, but it isn't the only one. Several other systems, including some that are provided only through licensed dental professionals, use similar digital planning and custom-fit trays. The brand matters less than two things: the quality of the treatment plan and the clinician supervising it. Aligners prescribed and monitored in person by a dentist or orthodontist, with proper records and regular check-ups, are very different from mail-order systems where no one examines your mouth.

Aligners vs. Braces at a Glance


Clear aligners

Traditional braces

Visibility

Nearly invisible

Visible, though ceramic is subtle

Removable

Yes

No

Eating restrictions

None, since trays come out

Avoid hard and sticky foods

Hygiene

Easier to brush and floss

More effort around brackets

Relies on patient compliance

Heavily

Less so

Emergency visits

Rare

Occasional broken brackets

Complex cases

Some limits

Very versatile


Common Questions

Do aligners hurt? Most people feel pressure for a day or two after switching trays. It's usually milder than the soreness after a braces adjustment.

Will they affect my speech? A slight lisp is common for the first few days and fades as the tongue adjusts.

How long does treatment take? Mild cases may finish in six months. More involved cases often take 12 to 18 months or longer.

Can I drink coffee with them in? It's best to remove them. Hot drinks can warp the plastic, and sugary or acidic drinks trapped under the trays increase the risk of cavities and staining.

Do I need a retainer afterward? Yes. Without one, teeth tend to drift back. Many people wear a clear retainer at night indefinitely.

Caring for Your Aligners

Rinse trays each time you remove them, brush them gently with a soft toothbrush and cool water, and avoid hot water, which can warp them. Always store them in their case. Many lost aligners end up wrapped in a napkin on a restaurant tray.

The Bottom Line

Clear aligners move teeth through the same biology as braces, just with a different tool. They offer comfort, convenience, and discretion, but they only work if worn consistently and supervised by a qualified dental professional. If you're disciplined about wear time and your case is a good fit, aligners can deliver a straighter smile with far less disruption to daily life.

Read more…

Choosing-the-Right-Dental-Implant-Specialist.jpg

Patients comparing implant quotes routinely find spreads of several thousand dollars for what sounds like identical treatment. Some of that is genuine market variation. Most of it is that the quotes describe different things.

An implant is three separate items

The post that replaces the root. The abutment that connects the post to what sits above it. And the crown you actually see and chew with.

Some practices quote all three. Some quote the surgical placement only, with the restoration billed later. When a figure looks dramatically lower than everything else, this is nearly always why, and the difference typically appears months into treatment.

Ask which components the number covers, in writing.

The items that may or may not be included

Extraction of the failing tooth, if it is still present. Socket preservation grafting at the time of extraction. Any ridge augmentation or sinus lift. The cone beam scan. Sedation, if used. The surgical guide, if the case is planned digitally. Follow-up appointments.

A complete quote covers all of these or explicitly excludes them. A vague quote leaves room for the total to grow, and the growth always happens after you have committed.

Why the scan is not optional

A standard x-ray shows height and tells you almost nothing about width, and width is what determines whether an implant fits without grafting.

A cone beam scan measures bone in three dimensions, shows density, and locates the nerve canal and sinus floor. Any quote given without one is an estimate based on incomplete information, and it is the leading cause of prices changing mid-treatment.

If a practice quotes you before imaging, ask what happens to the figure once the scan is done. The answer tells you how the quote was constructed.

Grafting is the biggest swing factor

Bone begins resorbing immediately after a tooth is removed, fastest in the first year. A site restored promptly usually needs nothing. A site left for five years often needs rebuilding, which adds months and a substantial sum.

This is why the same tooth costs different amounts depending on when you act, and why socket preservation at the time of extraction, which adds modestly to the extraction fee, is the highest-value decision in the whole sequence.

Where the cost genuinely varies for good reasons

Implant systems differ. Established manufacturers cost more and come with the advantage that components remain available in fifteen years when something needs servicing. Lesser-known systems can be considerably cheaper, and the risk is that parts become difficult to source later. Ask which system is being used and whether components will be obtainable long term.

Laboratory quality varies. A crown is a custom-made object, and the technician matters as much as the material.

Surgical experience varies. Volume matters in surgery, and asking how many implants a dentist places in a typical year is a fair question.

Insurance, realistically

Dental plans commonly cap annual benefits well below the cost of a single implant, and many exclude implants specifically while covering the crown or the extraction.

Ask the practice to run a pre-treatment estimate with your carrier. It takes a few weeks and it replaces guesswork with a number. Phasing treatment across two plan years is a legitimate way to use two annual maximums, and it fits naturally with a treatment that spans months anyway.

Treatment abroad, weighed honestly

Some patients consider having implant work done outside the country at lower cost. The surgery itself may be perfectly competent. The difficulty is follow-up: integration takes months, complications are managed locally, and components from an unfamiliar system may be hard to service here.

If you go this route, get the exact implant system and size documented in writing so a local dentist can work with it later.

What a well-planned case looks like

A scan. A written plan with the sequence and timeline in months. An itemized cost with a stated contingency if more grafting proves necessary. A discussion of the bridge and partial denture as genuine alternatives. And a clear answer about why the tooth was lost, because periodontal disease or a grinding habit will act on the replacement too.

Asking a dental office to provide that in writing before you pay a deposit is entirely normal, and practices that plan carefully produce it without difficulty.

Financing, and how to read it

Most practices offer third-party financing, and the terms range from genuinely interest-free promotional periods to arrangements that cost considerably more than the treatment.

Read what happens at the end of a promotional period. Some plans apply deferred interest retroactively across the entire original balance if any amount remains unpaid, which turns a manageable plan into an expensive one overnight.

Ask for the total repayment figure rather than the monthly payment. A practice quoting only a monthly number is describing affordability rather than price, and those are different things.

The comparison worth making

Do not compare headline numbers. Compare what is included, which system is used, whether a scan has been done, and what happens if the site needs more work than expected.

Two quotes built on the same assumptions can be compared. Two quotes built on different ones cannot, and the cheaper of those is usually the more expensive one by the time it is finished.

Read more…

Veneers are the most requested and least understood treatment in cosmetic dentistry. Patients arrive asking for them by name, often having decided before any examination, and the consultation becomes a negotiation rather than a diagnosis.

images?q=tbn:ANd9GcR_TksgDfsybwarZp9VbpGxTM5mmMQTTIVOezMivBqxigo3eYER_1Cu4uUF&s=10

Understanding what they actually do makes that conversation far more productive.

What a veneer is

A thin shell of porcelain bonded to the front surface of a tooth. It changes color, shape, and to a limited extent apparent position. It does not move teeth, it does not strengthen them meaningfully, and it does not fix anything happening below the gumline.

Most veneers require removing a layer of enamel to make room for the porcelain, typically a fraction of a millimeter but occasionally more where a tooth sits forward. That removal is permanent. From that point the tooth needs a veneer or crown indefinitely.

Minimal-preparation veneers exist and remove very little or nothing, but they only suit cases where the teeth are already slightly undersized or set back. A dentist telling you your case does not suit them is being accurate rather than upselling.

What they fix well

Discoloration that will not respond to whitening, including tetracycline banding and darkening from old root canal treatment. Teeth that are worn short at the edges. Small chips and irregular shapes. Small gaps between front teeth. Teeth that are slightly rotated or set marginally out of line.

For a patient with generally sound teeth and a longstanding dissatisfaction with their shape or color, well-planned veneers are transformative and durable.

What they fix badly

Real crowding. Porcelain changes the visible face of a tooth, not its position in the arch. Masking significant crowding requires either aggressive preparation, which sacrifices a lot of tooth, or accepting a result where the teeth look bulky. Straightening first, then doing far less restorative work, is nearly always the better plan and often costs less overall.

Gum problems. If the tissue is inflamed or receding, it will continue to recede after veneers are placed, exposing the margins within a few years. Periodontal health has to come first.

A bite that is causing the damage. If your front teeth are worn short because your back teeth are not supporting the bite, porcelain placed into that same force will chip. The bite has to be assessed and often managed before restorations go on, or the case fails on schedule.

The steps that separate a good case from a regrettable one

Photographs and a scan or impressions. A wax-up or digital design of the proposed result, built before anything is prepared. And a trial: that design converted into a temporary mock-up placed over your existing teeth so you can look at it in a mirror, in daylight, for several days.

That trial is where changes cost nothing. Wanting the teeth a millimeter shorter is a conversation at the mock-up stage and a full remake after bonding.

Any plan for six or more veneers without a preview stage is asking you to approve something you have not seen.

The provisional phase

After preparation, temporary veneers made from the approved design are worn while the porcelain is made. Live in them. Eat, speak, take photographs, and notice anything that catches your lip or feels wrong.

Report it. Temporaries are designed to be modified. Once the final restorations are bonded, changes mean remaking them.

Longevity and maintenance

Well-made porcelain veneers commonly last ten to fifteen years and often longer. They do not stain the way composite does, and they hold their polish.

What ends them early is force. Grinding chips porcelain, and any patient who clenches needs a night guard as part of the plan rather than as an afterthought. Biting nails, opening packaging with your teeth, and chewing ice will all shorten the life of the work.

The margins where porcelain meets tooth remain vulnerable to decay, so hygiene matters as much afterward as before. Veneers are not a way to stop worrying about your teeth.

The cheaper alternatives worth trying first

Whitening removes nothing and costs a fraction. If your only complaint is color and your teeth are otherwise sound, start there.

Composite bonding is additive, reversible, and repairs chips and small gaps in one appointment. It stains and chips over five to seven years, but it is inexpensive to renew and it keeps every option open.

A dentist who suggests trying the conservative version first is not being unambitious. They are preserving enamel you cannot get back.

Choosing who does the work

Ask to see cases they have done personally, including photographs taken years afterward rather than on delivery day. Ask which laboratory they use and whether the technician does custom shade work. Ask what happens if you dislike the mock-up.

Working with a dentist who insists on the design and trial stages, even when you would rather move quickly, is the strongest predictor of a result you will still be happy with in a decade.

Read more…

images?q=tbn:ANd9GcQdTZ2D1-RUqa14izp5WYQSadt8p1cON-TncV7wBQEB4Y97Lrzg8Uq0bSPJ&s=10

There is a version of cosmetic dentistry that solves the specific thing bothering you, and a version that replaces your entire smile because the specific thing was hard to match. The gap between them is often tens of thousands of dollars, and which one you get depends heavily on the dentist's skill and honesty about single-tooth work.

Why one tooth is harder than eight

Matching a single restoration to the teeth beside it is the most technically demanding thing in aesthetic dentistry. Natural teeth are not one color. They are translucent at the edge, more opaque at the body, often slightly warmer near the gum, and they carry small characteristics, faint lines, subtle spots, that the eye reads without noticing.

Doing eight veneers sidesteps the problem entirely, because everything is made to match everything else. That is why it gets recommended. Sometimes that is genuinely the right plan. Often it is the easier one.

A dentist who is willing to attempt a single central incisor, and who has a lab technician capable of it, is offering something more difficult and considerably more conservative.

What single-tooth matching actually requires

Shade taking under proper lighting, ideally with photographs including a shade tab held beside the tooth so the technician sees the relationship rather than a written note. Better practices send multiple photographs with different exposures.

Sometimes a custom shade appointment at the laboratory, where the technician looks at your tooth directly. This is not available everywhere and it is the gold standard for a difficult front-tooth match.

And a willingness to try again. Occasionally a first attempt comes back not quite right, and the correct response is to remake it rather than to talk you into accepting it or into treating the neighbors.

The chipped edge

The most common single-tooth complaint is a chipped incisal edge, usually from trauma, biting something hard, or years of grinding. Composite bonding repairs this in one appointment, usually without anesthetic and often without removing any tooth structure.

It is inexpensive, entirely reversible, and it will need renewing in perhaps five to seven years as the composite stains at the margin. That is a good deal. Being quoted a crown for a small chip is worth a second opinion.

The dark tooth

A single tooth that has darkened years after a root canal is a specific problem with a specific solution. Internal bleaching places whitening agent inside the tooth rather than on it, and it often lightens the tooth substantially over a few appointments.

It is far more conservative than the alternative, which is a crown, and it costs a fraction as much. It does not always work completely, and it can relapse over years, but it is nearly always worth trying first. A plan that goes straight to a crown for a discolored root-canalled tooth has skipped a step.

The tooth that sits slightly out of line

Minor rotation or a tooth positioned slightly forward or back can sometimes be masked with bonding or a veneer, but the more conservative answer is often limited orthodontic treatment. A few months of aligners can move the tooth into position, after which little or no restorative work is needed.

This is more common than patients realize, and it preserves the tooth entirely. The tradeoff is time, which is why it gets skipped when patients arrive wanting a result before an event.

When doing everything genuinely is right

If several front teeth are worn short from grinding, the whole segment has to be rebuilt together because the length relationship between them is the thing being corrected. If the existing crowns are old and mismatched, replacing one leaves you with a mismatched set. If the bite itself is the problem, isolated restorations will keep failing.

In those cases comprehensive work is the correct plan. What you want is a dentist who explains why your case is one of them, in terms specific to your mouth.

Questions that surface the difference

Ask whether the problem can be solved by treating only the tooth that bothers you, and if not, why not. Ask whether bonding could be tried before porcelain. Ask what the plan is if the shade does not match on the first attempt, and who pays for the remake.

Ask to see photographs of single-tooth cases they have done, especially anterior ones. Practices that do this work well are usually proud of it, because it is difficult.

Choosing conservatively

Working with a cosmetic dentist who will treat one tooth when one tooth is the problem tends to save both money and enamel, and it leaves every option open for later.

Enamel does not regenerate. Every conservative choice you make now is a choice you still have available in fifteen years, and the patients who end up happiest with their teeth in their sixties are usually the ones whose dentists did the smallest thing that worked.

Read more…

images?q=tbn:ANd9GcS1gcZuHBpPHQKydFJMRzKnti5eJXIWYOdWkrP4xn5vZMI5IVPMK7-va1k&s=10

A single missing tooth is the most common implant scenario and the one where patients are most likely to be steered toward more treatment than the situation requires. It is worth understanding the options clearly before you sit down for a consultation.

Why the gap matters even when it does not show

A missing back tooth is easy to ignore. Nothing hurts, nobody sees it, and chewing adapts. The consequences develop slowly.

Teeth adjacent to a gap drift into it over months and years, tipping rather than moving bodily, which creates food traps and awkward angles that are difficult to clean. The tooth opposing the gap has nothing to meet and gradually over-erupts, dropping down or up into the space. By the time you decide to replace the missing tooth, there may not be room for it without addressing the teeth that moved.

The bone where the root was also resorbs, fastest in the first year. A site restored promptly usually needs no grafting. The same site five years later often does.

The three real options

An implant replaces the root and the crown independently of the neighboring teeth. It is the only option that preserves the bone through loading, and it does not require touching healthy teeth on either side.

A fixed bridge spans the gap using the adjacent teeth as supports. This means those teeth are reduced substantially, which is a significant cost when they are healthy and untouched. It is quicker and often less expensive up front, and it remains a reasonable choice when the neighboring teeth already need crowns for other reasons.

A removable partial denture is the least expensive and the least satisfying. It comes out, it moves slightly, and it puts load on the remaining teeth through clasps. For a single tooth it is usually a temporary measure rather than a plan.

Doing nothing is a fourth option and occasionally the right one, particularly for a missing second molar where the drifting risk is lower. A dentist willing to say so is telling you something useful.

When an implant is the clear answer

Healthy, unrestored teeth on either side of the gap. Adequate bone, or a site that can be grafted straightforwardly. A patient who does not smoke and whose gum health is stable. A visible tooth where appearance matters.

In that situation, the argument for a bridge is weak, because the bridge requires damaging two healthy teeth to solve a problem that does not involve them.

When it is not

If the adjacent teeth already have large fillings or failing crowns, a bridge may accomplish two things at once and represent better value. If bone volume is very limited and grafting would be extensive, the calculation changes. If a patient has active periodontal disease, that needs treating first regardless of which option is chosen.

Cost matters too, and it is legitimate to choose a bridge because an implant is out of reach this year. What is worth avoiding is choosing a bridge without being told what it costs the neighboring teeth.

The timeline for one tooth

If the tooth is still present, extraction with socket preservation comes first, then three to four months of healing. Implant placement follows, then three to six months of integration. Then the abutment and crown across two or three visits.

Roughly six to nine months in total for a straightforward case, sometimes shorter when the site is already healed and the bone is good. A temporary tooth covers the visible zone throughout.

What a good consultation covers

A cone beam scan, not just a flat x-ray, because bone width cannot be assessed any other way. A discussion of all three options with real costs. An assessment of why the tooth was lost, because if the cause was periodontal disease or a grinding habit, the same forces will act on the replacement.

And a clear all-in figure. Implant quotes are commonly fragmented across the post, abutment, crown, extraction, grafting, and imaging, and comparing two quotes that include different components is meaningless.

What happens after the crown goes on

Implants do not decay, which leads a lot of patients to assume they need less attention than natural teeth. The opposite is closer to true. The tissue and bone around an implant are fully susceptible to inflammation, and once bone is lost around a post it does not come back easily.

Daily cleaning around the restoration matters, and the technique is slightly different from flossing a natural tooth. Professional maintenance should use instruments appropriate for implant surfaces. Ask what the recall interval will be and what those visits involve, because the twenty-year outcome is decided by that routine rather than by the surgery.

Getting an unhurried assessment

The consultation you want is one where doing less is on the table. Talking it through with a local dentist who handles both the surgical and restorative sides can simplify this considerably, because one person is accountable for the outcome rather than two offices coordinating.

Ask what they would do if it were their own tooth, and ask what happens if you wait a year. Both answers are informative, and a dentist who tells you that waiting is fine for your particular gap has just given you the most valuable information in the appointment.

Read more…

The failures in cosmetic dentistry almost never happen in the chair. They happen in the planning, or in the absence of it, weeks before any tooth is touched. A patient who is unhappy with their result usually got competent execution of a design nobody properly agreed on.

personalized-treatment-plans-dental-consultation-1.jpg

Here is what a well-run cosmetic process looks like before the drill comes out.

The conversation about what is actually bothering you

This sounds obvious and it is skipped constantly. People arrive saying they want a better smile. That could mean color, shape, length, crowding, the amount of gum showing, a single tooth that has always sat oddly, or something about how the smile relates to the rest of the face.

A dentist who starts by asking you to point at what you dislike in a photograph of your own teeth will end up somewhere very different from one who starts by describing a package. If your concern is one discolored front tooth from an old root canal, the answer is likely one crown or internal bleaching, not eight veneers.

Photographs and records

Expect a full photographic series: full face smiling, retracted views of the teeth, close-ups of the front section, and views of how the teeth meet. Expect impressions or a digital scan, and x-rays to confirm that the teeth underneath are healthy enough to restore.

These are not formalities. The photographs are how the dentist assesses tooth proportion, midline, and the relationship between your smile line and your lip. The scan is how the proposed shape gets designed and tested outside your mouth.

The wax-up or digital design

This is the step that separates careful cosmetic dentistry from the rest. Before anything is prepared, the proposed result is built, either physically in wax on a model of your teeth or digitally on a scan.

You should see it. Better still, you should be able to try it. A mock-up can be made from that design and placed temporarily over your existing teeth, without any preparation, so you can look in a mirror, take photographs, show your family, and live with it for a few days.

That trial is where changes are cheap. Wanting the teeth slightly shorter is a five-minute conversation at the mock-up stage and a full remake after the porcelain is bonded.

The health assessment nobody markets

Cosmetic work placed onto an unhealthy foundation fails. Active gum disease has to be treated first, because inflamed tissue recedes and will expose the margins of new restorations within a couple of years. Decay under existing fillings must be addressed. Untreated grinding must be managed.

If your smile concern is partly that your gums show more than you would like, that is a tissue question rather than a tooth question, and the answer may involve gum recontouring rather than restorations. A plan that treats every aesthetic complaint as a porcelain problem is not diagnosing.

Choosing the least invasive option that works

Ranked by how much natural tooth is sacrificed: whitening removes nothing, bonding removes little or nothing, veneers remove a layer of enamel, crowns remove considerably more. A good plan starts at the top of that list and moves down only as far as necessary.

Straightening first often reduces the work needed. A patient with crowded, discolored front teeth might be quoted eight veneers, when six months of aligner treatment followed by whitening and one bonding repair achieves a similar result at lower cost while keeping the teeth intact.

Any plan that jumps straight to the most invasive option without discussing the alternatives deserves a second opinion.

The provisional phase

For larger cases, the teeth are prepared and temporary restorations are placed, made from the approved design. You wear them for a period, and this is your last and best opportunity to identify problems: a tooth that catches your lip, a length that makes speech awkward, an edge that feels wrong.

Report anything that bothers you during this phase. Temporaries are designed to be modified. The final restorations are not.

What it costs to change your mind later

Reversibility is worth pricing into the decision. Whitening can simply be stopped. Bonding can be removed and the tooth returns to roughly its original state. Veneers cannot be undone, and a tooth prepared for one will need a restoration permanently.

That is not a reason to avoid veneers when they are the right treatment. It is a reason to be certain, and to notice when a plan quietly moves you from a reversible option to an irreversible one without that being discussed.

Finding the right practice for this

Ask to see cases the dentist has done personally, ideally with photographs taken years after delivery rather than on the day. Ask how they handle it if you dislike the result at the trial stage. Ask what happens to the fee if the case needs remaking.

Working with a cosmetic dentist who insists on the mock-up stage, even when you are impatient to get started, is a good sign rather than a delay. The practices that skip previews are the ones producing the results people quietly regret.

Cosmetic dentistry done properly is slow at the front end and boring in the middle. That is what makes it look effortless at the end.

Read more…

Most people hear the phrase bone graft and picture something far more dramatic than what actually happens. In dentistry it is usually a routine, small-volume procedure done under local anesthetic, and it is one of the main reasons implant treatment is available to people who would have been turned away twenty years ago.

194ace_4fffa6a4b42740da814358d290542acb~mv2.jpg

Understanding it makes implant quotes far easier to read, because grafting is frequently the difference between two very different prices for what sounds like the same treatment.

Why the bone disappears in the first place

Jawbone maintains itself through use. A natural tooth root transmits chewing force into the bone around it, and that stimulation is what tells the body to keep the bone there. Remove the tooth and the signal stops.

The loss is fastest in the first six to twelve months after extraction and continues slowly for years. Width goes before height, which matters because an implant needs a certain thickness of bone on all sides to be stable and to stay covered by healthy tissue.

This is why the timing of your decision affects the cost. A site grafted at the time of extraction usually needs nothing further. The same site left empty for five years may need substantially more work to rebuild.

Socket preservation, the cheapest version

When a tooth is removed and an implant is planned, graft material is often placed into the empty socket immediately and covered with a membrane. This is socket preservation, and it adds a modest amount to the extraction fee.

It is the highest-value grafting in dentistry. Rather than rebuilding lost bone later, it holds the shape of what is already there while the site heals, typically over three to four months. Anyone having a tooth removed who might want an implant eventually should ask about it before the extraction, not after.

Ridge augmentation and sinus lifts

When the site has already collapsed, more is required. Ridge augmentation adds width or height to a thin area of jaw, using graft material held in place by a membrane and sometimes secured with small screws or a titanium mesh. Healing runs four to nine months depending on the volume added.

In the upper back jaw there is a specific problem: the maxillary sinus sits directly above the molar roots, and once those teeth are gone the sinus tends to expand downward into the space. A sinus lift raises the sinus membrane and places graft material underneath it to create the bone height an implant needs. It can be done through a small window in the side of the jaw for larger cases, or through the implant site itself when only a few millimeters are needed.

Both are established procedures with high success rates. Both add months to the timeline, and both should be identified at the planning stage rather than discovered mid-treatment.

What the graft material is

Several options, all routine. Material can come from your own body, from a processed human donor source, from an animal source (usually bovine), or from a synthetic mineral. Each behaves slightly differently in how quickly it resorbs and is replaced by your own bone.

Patients often want to know which is best. The honest answer is that the choice depends on the site and the volume needed, and that all of the commonly used options are well studied. What matters more is the diagnosis behind the plan and the technique used to place it.

The scan that makes the plan honest

None of this can be assessed from a standard x-ray, which is a flat image of a three-dimensional problem. A cone beam scan measures bone width, height, and density, and locates the nerve canal in the lower jaw and the sinus floor in the upper.

A consultation that quotes implants without a scan is quoting a guess. This is the single most common reason a price changes partway through treatment, and it is entirely avoidable.

Reading a quote once you know this

Ask whether the figure includes extraction, socket preservation, any ridge or sinus work, the implant itself, the abutment, and the final crown. Ask what happens to the price if the site turns out to need more grafting than the scan suggested.

A practice that answers those in detail is one that has planned the case. Working with a local dentist who does the surgical and restorative phases under one roof tends to produce fewer surprises, because the person deciding whether the site needs grafting is the same person who has to make the final crown fit.

The takeaway for anyone facing an extraction

If a tooth is coming out and there is any chance you will want to replace it, raise grafting before the extraction appointment. It is the cheapest, simplest point in the entire process to protect your options, and it is the one that most often gets missed.

Read more…

There is a point in complex dental work where the question stops being what to do and becomes who should do it. Most patients never learn that point exists. They get quoted for a full set of crowns by a general dentist, or a bridge that has to survive twenty years of chewing, and they assume dentistry is dentistry.

Local-Family-Dental-Practice.jpg

It is not. Prosthodontics is a recognized dental specialty requiring three additional years of training after dental school, and it exists specifically because rebuilding a bite is a different discipline from maintaining one.

What a prosthodontist actually does

The specialty covers the replacement and restoration of teeth: crowns, bridges, dentures, implant restorations, and the full-mouth reconstructions that combine all four. The training concentrates on how teeth meet, how force distributes across an arch, and how to design restorations that survive the loads a jaw generates thousands of times a day.

That last part is the whole game. A crown that looks perfect and sits fractionally high will fail, and it will take the opposing tooth with it. A denture that fits the gum tissue but ignores how the jaw closes will rock, sore up the ridge, and end up in a drawer. These are engineering problems as much as dental ones.

The cases where the distinction matters

Plenty of restorative work belongs squarely with a good general dentist. A single crown on a molar, a straightforward filling, a routine bridge in a healthy mouth. Many general dentists do this work beautifully and have done it for decades.

The cases that benefit from specialty training tend to share a few features. Multiple teeth being restored at once, so the bite is being rebuilt rather than repaired. Significant existing wear, where the original tooth height is gone and someone has to decide what to restore it to. Failed previous work, where the last attempt did not hold and the reason matters. Implants supporting several teeth, where load distribution determines whether the case lasts. And full or near-full arch replacement, where there is no natural reference left to copy.

The wear question nobody explains

A common scenario: a patient in their fifties whose front teeth have shortened over decades of grinding. They want them back to the original length. The general answer is veneers. The specialist answer starts with a different question, which is where the bite currently closes and whether lengthening those teeth will cause them to strike the lowers on every chew.

Sometimes the answer is that the bite has to be opened first, which is a substantially larger undertaking than eight veneers. Patients who get the veneers without that assessment often return within two years with chipped restorations, and the second attempt is harder than the first because there is less tooth left to work with.

Cost, and why the cheaper quote sometimes is not

Specialty care usually carries a higher fee for the same-sounding procedure. Comparing quotes line by line is reasonable, and it is also where people get burned. A full-arch case quoted at a substantial discount is usually cutting something: the diagnostic workup, the provisional phase where you live in temporary restorations to test the design, the lab, or the material.

The provisional phase is the one to protect. Test-driving a proposed bite for a few weeks before it is made permanent is the single best insurance against a reconstruction that looks right on the model and feels wrong in your mouth. Cases that skip it are cheaper because the risk is being transferred to you.

What a first consultation should include

Expect photographs, a full series of x-rays, often a cone beam scan if implants are involved, and impressions or a digital scan that lets the dentist study your bite outside your mouth. Expect a conversation about what caused the current situation, because a reconstruction placed into an unaddressed grinding habit will fail on schedule.

Expect, also, more than one option. Nearly every complex case has a conservative version and an ideal version, and a good consultation lays out both with honest tradeoffs rather than steering hard toward the larger one.

Coordinating between generalist and specialist

The best outcomes in this area usually involve both. Your general practice handles hygiene, prevention, and the routine work, and knows your history. The specialist handles the reconstruction. They share records and agree on the plan before anything is prepared.

If you are trying to figure out which side of that line your situation falls on, start with the practice that knows your mouth, because an experienced family dentist can usually tell you within a single appointment whether what you need is a crown or a plan. Being told plainly that you do not need specialty care is a perfectly good outcome for a consultation.

The timeline is longer than you expect

Full reconstruction is measured in months, not weeks. Diagnostic phase, provisional phase, adjustments, then final restorations. Anyone promising a complete rebuild in two visits is skipping steps that exist for a reason.

That timeline is the strongest argument for getting the assessment before the situation becomes urgent. Decisions made under pain pressure are worse decisions, and in Ponte Vedra Beach as anywhere else, the patients with the best long-term results are the ones who started the conversation while they still had time to think about it.

Read more…

Single-Sitting-Root-Canal.jpg

Root canals have a reputation built almost entirely on how they were performed decades ago. The modern procedure is routine, generally comfortable, and it saves teeth that would otherwise be extracted. Knowing what is happening removes most of the dread.

What the treatment is for

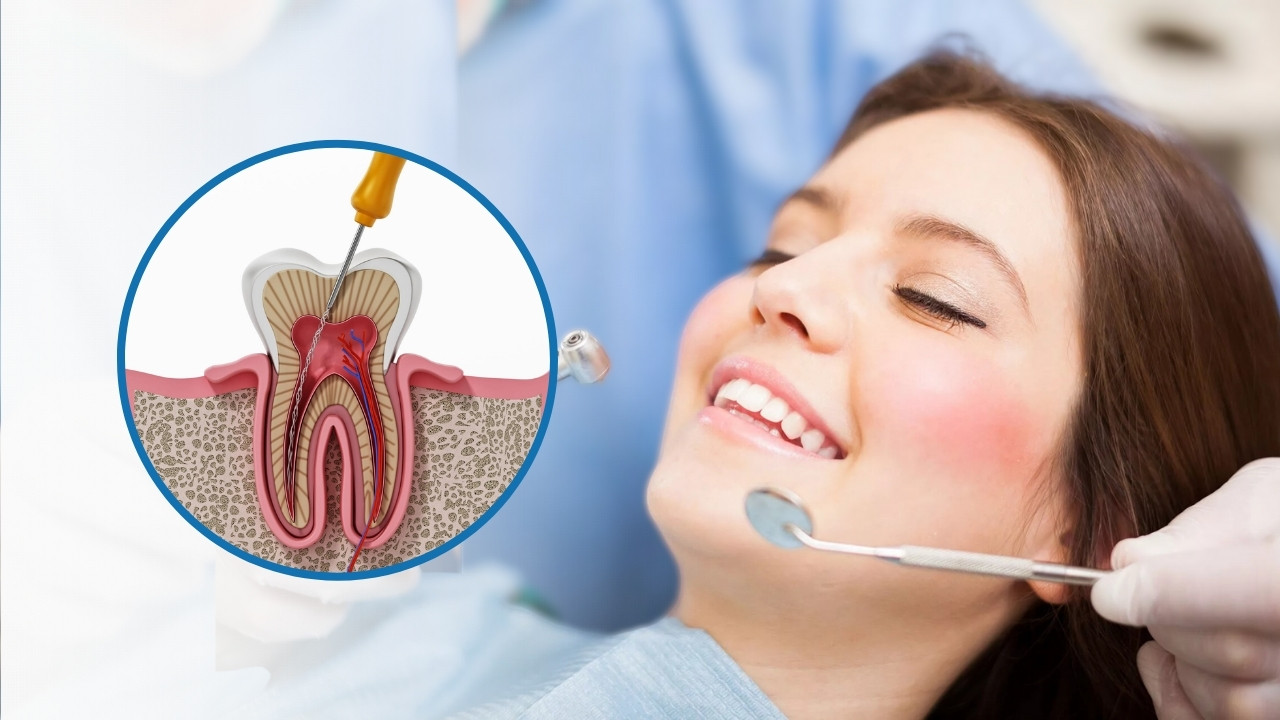
Inside every tooth is a chamber containing nerve and blood vessels, extending down through canals in each root. When bacteria reach that tissue, through deep decay, a crack, a failing restoration, or trauma, the tissue becomes inflamed and eventually dies.

Once that happens the infection spreads out through the tip of the root into the surrounding bone, forming an abscess. The tooth cannot heal on its own, and antibiotics do not reach the inside of the tooth in meaningful concentration, which is why they control symptoms temporarily and the problem returns.

Root canal treatment removes the affected tissue, cleans and shapes the canals, and seals them so bacteria cannot recolonize.

What the symptoms are

Lingering pain to hot or cold, particularly discomfort that continues for more than thirty seconds after the stimulus is removed.

Pain that wakes you, throbs, and worsens when you lie down, because blood pressure in the head increases.

Tenderness to biting or pressure. Swelling of the gum near the tooth, sometimes with a small bump that discharges and then reappears. Darkening of a single tooth.

Sometimes there are no symptoms at all and the problem is found on a routine x-ray as a dark area at the root tip. That is common with teeth that died some time ago.

What the appointment is like

Local anesthetic first, and this is the part most people are anxious about. A tooth that is already inflamed can be harder to numb fully, so tell the dentist if you feel anything. There are supplementary techniques available and no reason to endure discomfort.

A rubber dam is placed, isolating the tooth. This keeps the field clean and stops anything from reaching the back of your throat. It also makes the procedure considerably more predictable.

The chamber is opened, the canals are cleaned with fine instruments and irrigating solutions, shaped, and then filled with a sealing material. The access opening is closed with a temporary or permanent filling.

Front teeth with a single canal are quicker. Molars, with three or four canals and often complex anatomy, take longer and are sometimes split across two appointments.

For most patients the experience is comparable to having a large filling, other than the duration.

Afterward

Tenderness to biting for a few days is normal, particularly if there was an abscess, and responds to over-the-counter anti-inflammatory medication.

Severe pain, swelling, or fever afterward is not routine and warrants a call.

The tooth is no longer sensitive to temperature, because the nerve is gone. It also becomes more brittle, having lost internal structure and hydration, which leads directly to the next point.

The crown afterward is not optional

Back teeth that have had root canal treatment need full coverage. A crown holds the remaining structure together and distributes chewing force across the whole tooth rather than concentrating it on weakened walls.

Root-canalled molars left without crowns are among the most common vertical root fractures, and a vertical root fracture generally ends the tooth. All the money spent on the root canal is lost.

If you have had a root canal in the past and never had the crown placed, that is worth raising at your next appointment rather than waiting for a symptom.

Front teeth sometimes manage without full coverage if the access opening is small and the tooth is otherwise intact. Ask which category yours is in.

Success, retreatment, and specialists

Root canal treatment succeeds in the large majority of cases and treated teeth commonly last for decades.

When one fails, usually because a canal was missed, the seal broke down, or new decay reached the filling, retreatment is often possible: the existing filling is removed, the canals are recleaned, and the tooth is resealed. Alternatively an apicoectomy removes the tip of the root surgically.

Endodontists are specialists who complete additional years of training focused on this work and who have operating microscopes and specialized equipment. Referral makes sense for complex anatomy, retreatment, teeth with calcified canals, and cases where a general dentist encounters difficulty.

Plenty of straightforward root canals are handled well in general practice. A dentist who refers out the complicated ones is showing judgment.

The alternative, honestly

The alternative to a root canal is extraction. That is cheaper on the day and more expensive over time, because replacing the tooth with an implant or a bridge costs considerably more than the root canal and crown would have.

Keeping your own tooth is nearly always the better outcome when the prognosis is reasonable. Where it is not, a dentist saying so plainly is doing you a service.

Discussing it with a dentist who explains why the tooth is or is not worth saving, in terms of the specific remaining structure, gives you the information to decide rather than a decision to accept.

Read more…

Picture1-1-1024x683.jpg

These two treatments get compared constantly and the comparison is usually framed wrongly, as cheap versus good. They are different tools with different lifespans and different consequences, and for a lot of cases bonding is the better clinical choice rather than the compromise.

What each one is

Composite bonding is tooth-colored resin applied directly to the tooth and shaped by the dentist in the chair, then hardened with a light. One appointment, no laboratory, usually no anesthetic.

A porcelain veneer is a thin shell made in a laboratory from a scan or impression and bonded to the front of the tooth. Two appointments minimum, usually requiring removal of a layer of enamel first.

The reversibility difference

This is the single most important distinction and it is often glossed over.

Most bonding requires little or no removal of natural tooth. If you dislike it, it can be removed and the tooth returns to roughly its original state. If it chips in four years, it is repaired in an appointment.

Veneers usually require preparation. From that moment the tooth needs a veneer or crown permanently. That is not an argument against them, but it is an argument for being certain, and for asking directly how much enamel a specific plan involves, because it varies substantially between cases and between dentists.

Where bonding is clearly right

A chipped incisal edge, which is the most common single-tooth cosmetic complaint. Small gaps between front teeth. Reshaping a tooth that is slightly small or sits marginally out of line. Repairing worn edges in a younger patient. Filling in the small triangular gaps that sometimes appear between teeth after orthodontic treatment.

For these, bonding is conservative, quick, and inexpensive, and it keeps every option open.

Where porcelain earns its cost

Widespread discoloration that will not respond to whitening. Multiple teeth being restored together, where the shapes and lengths need to relate to each other. Teeth with existing large restorations where there is not enough sound tooth for bonding to hold. Cases where bonding has been tried and repeatedly failed.

Porcelain resists staining far better, holds its polish for years, and in skilled hands produces a translucency composite cannot match.

The honest lifespan comparison

Composite bonding realistically lasts five to seven years before it needs renewing, less under heavy grinding. It picks up stain at the margins where it meets enamel, and it chips.

Porcelain veneers commonly last ten to fifteen years and often longer.

The relevant comparison is not the fee on the day. It is cost over twenty years, weighed against how much tooth each option removes. For a patient in their twenties with a chipped edge, two rounds of bonding across fifteen years is usually a better outcome than a veneer placed at twenty-five, because the enamel is still there at forty.

What ends both of them early

Grinding, overwhelmingly. It chips porcelain and wears through composite, and it happens at night to people who mostly do not know they do it.

A night guard belongs in the plan from the beginning for anyone showing the signs: flattened cusps, worn front edges, notches at the gumline, scalloping along the tongue. It costs a fraction of a single restoration.

Habits matter too. Biting nails, opening packaging with your teeth, and chewing ice will shorten the life of either material.

The case for trying the smaller thing first

Whitening removes nothing at all. If color is the whole complaint and the teeth are otherwise sound, that is the entire answer.

For genuine crowding, straightening first usually reduces the restorative work substantially and often lowers the total cost while leaving the teeth intact.

A dentist who suggests the conservative version first is not being unambitious. They are preserving something you cannot replace.

The preview stage for anything larger

For multiple veneers, the proposed result should be designed as a wax-up or digitally and then converted into a mock-up worn temporarily over your existing teeth before anything is prepared.

Look at it in daylight, photograph it, live with it for a few days. Changes at that stage cost nothing; changes after bonding mean remaking the case.

Any plan for six or more veneers without a preview is asking you to approve a result you have not seen.

Choosing the dentist rather than the material

Skill matters more in bonding than most people realize, because it is sculpted freehand in the mouth rather than made in a laboratory. Well-executed composite is genuinely difficult and a dentist who does it well is worth finding.

Ask to see their own cases, including bonding, photographed years after placement rather than on the day.

Working with a local dentist who will tell you that bonding is the right answer for your single chipped tooth, rather than quoting a set of eight veneers because it is easier to match, is what leaves you with more of your own teeth at sixty.

Read more…

ChatGPTImageJan20202606_57_56P.jpeg

Whitening is straightforward on its own. It becomes complicated the moment there is any other dental work involved, and the sequence errors people make are expensive and entirely avoidable.

The rule that governs everything

Whitening changes natural enamel and does nothing to fillings, crowns, veneers, or bonded composite.

That single fact determines the correct order of operations. Whiten first, wait for the shade to stabilize, then match any restorations to the final result. Do it the other way round and you end up with restorations that read darker than the teeth around them, and the only remedy is replacing them.

The specific mistake to avoid

A patient needs a crown on a front tooth and also wants whiter teeth. The crown is made first, matched to the current shade. Six months later they whiten, and now the crown is conspicuously darker than everything beside it.

The crown cannot be bleached. It has to be remade, at full cost, and the patient has effectively paid twice.

If you are contemplating whitening at any point in the next year or two and restorative work is planned on a visible tooth, say so before the shade is taken. It is a thirty-second conversation that prevents a four-figure problem.

How long to wait between whitening and restoring

Shade continues to settle for a period after whitening finishes, and bonding strength is temporarily reduced immediately afterward because of residual oxygen in the enamel.

Two weeks is a common minimum before taking a final shade or bonding anything. Some dentists prefer longer. Ask, because a restoration matched on the day whitening finishes may end up lighter than the teeth once they settle.

The options, and which suits whom

In-office whitening uses a stronger gel with the gums protected and produces a visible result in one appointment. It suits people with a deadline and those who will not persist with trays at home.

Custom take-home trays are made from an impression of your teeth so the gel is held against the surface rather than diluted by saliva. Worn over one to two weeks they achieve comparable results, usually for less, and you keep the trays for touch-ups indefinitely. For most people this is the better value, and the trays are what make maintenance cheap for years afterward.

Many practices combine both: an in-office session for a fast start, then trays for maintenance.

Over-the-counter strips work slowly and unevenly, mostly because they do not fit the teeth and the gel washes away.

What will not respond

Intrinsic discoloration does not bleach. That includes the gray or banded shading from tetracycline exposure in childhood, from excessive fluoride during tooth development, and the darkening of a single tooth years after root canal treatment.

The last one has its own answer: internal bleaching, where the agent is placed inside the tooth rather than on it. It often lightens substantially across a few appointments, costs a fraction of a crown, and removes no tooth structure. It is worth attempting before considering coverage.

Being told at the outset that your discoloration is intrinsic saves a wasted course of treatment.

Sensitivity, managed rather than endured

Temporary sensitivity is common, not evidence of damage, and resolves within days of finishing.

It can be reduced: a potassium nitrate desensitizing gel before and during treatment, shorter wear times, longer gaps between sessions, and sensitivity toothpaste for a couple of weeks beforehand.

Patients with existing recession, exposed root surfaces, or untreated decay feel it considerably more, which is the main argument for an examination before whitening rather than after. Gel reaching a cavity or a leaking margin is genuinely uncomfortable.

Making it last

One to three years is typical, driven mostly by coffee, tea, red wine, and dark sauces.

Rinsing with water after those helps a great deal. Keeping your trays makes touch-ups inexpensive. And avoid brushing immediately after anything acidic, including wine and citrus, since enamel is temporarily softened and brushing then removes more than it cleans. Thirty minutes is enough.

What to avoid entirely

Abrasive and charcoal products remove surface stain by removing surface enamel. The short-term brightening is real and so is the long-term cost, because thinning enamel lets the yellower dentin underneath show through. Enamel does not regenerate.

Whitening around braces and aligners

Another sequencing question worth raising early. Whitening during fixed brace treatment is generally deferred, because the brackets cover part of each tooth and the result is uneven once they come off.

Aligner treatment is different, since the trays come out and can in some cases double as whitening trays. Ask whether that is appropriate for your case, because it can save a separate course of treatment.

Either way, the sensible point to whiten is after orthodontic treatment finishes and before any restorative work is matched.

Getting the sequence planned

If you have any restorative or cosmetic work in mind, raise whitening at the planning stage rather than treating it as a separate decision later.

A local dentist who asks about your whitening intentions before taking a shade is thinking about the whole sequence rather than the appointment in front of them, and that is what keeps you from paying for the same crown twice.

Read more…

Childhood tooth decay is common, but it is also one of the most preventable problems in all of medicine.

images?q=tbn:ANd9GcQ6xyVF5PXmToIkTixTMlQM-Px9DM-_TfEl0Jl9WLOsUm3LBY-YQp6eXdhq&s=10

Tooth decay is the most common chronic disease of childhood, and yet it is very nearly preventable. That gap between how common cavities are and how avoidable they are usually comes down to a handful of everyday habits. The good news for parents is that protecting your child's teeth is neither complicated nor expensive.

How cavities form

Cavities are not caused by sugar directly. They are caused by bacteria that live in the mouth and feed on sugars and starches, producing acid as a byproduct. That acid attacks the enamel, and over time it eats through, creating a cavity. The two levers a parent can pull are clear: reduce how often the bacteria are fed, and remove them regularly through cleaning. Everything else is a variation on those two ideas.

Frequency matters more than quantity. A child who sips juice or grazes on crackers throughout the day keeps the mouth under constant acid attack, which is far more damaging than the same amount of sugar eaten at once. Water between meals, and limiting sugary drinks to mealtimes, makes a real difference.

The daily habits that work

Brush twice a day with a fluoride toothpaste, using a smear the size of a grain of rice for toddlers and a pea-sized amount for older children. Young kids lack the coordination to brush well on their own, so parents should help or supervise until around age seven or eight. Once teeth touch, begin cleaning between them daily. And never send a baby to bed with a bottle of anything but water, since pooling milk or juice overnight is a leading cause of early decay.

Two professional tools deserve special mention. Fluoride strengthens enamel and can even reverse the earliest stages of decay, which is why dentists often apply it at checkups. Dental sealants, thin protective coatings painted onto the chewing surfaces of the back teeth, block the deep grooves where cavities most often begin and can dramatically reduce decay in those teeth.

Regular visits tie all of this together. A dentist for kids can apply fluoride and sealants, catch early decay while it is still easy to treat, and coach both you and your child on technique in a setting designed to keep young patients comfortable.

Turning brushing into a habit that sticks

Knowing the rules is easy. Getting a child to follow them twice a day, every day, is the real challenge. A few tricks help. Brushing alongside your child models the behavior and lets you check their technique, and a two-minute song or timer turns the clock into a game rather than a chore. Letting a child pick their own toothbrush or flavor of toothpaste gives them a small sense of ownership that pays off in cooperation.

Consistency beats intensity. A calm, predictable routine at the same times each day, tied to existing habits like getting dressed in the morning and putting on pajamas at night, helps brushing become automatic. Praise works better than pressure, and small reward charts can motivate younger children through the early weeks. The goal is not a perfect performance every time but a habit so ingrained that skipping it feels strange, a habit that will protect their teeth long after they stop needing your reminders.

Drinks deserve particular attention, because they are an easy place to make a big difference. Juice, soda, and sports drinks bathe the teeth in sugar and acid, and sipping them slowly over an afternoon is worse than finishing them quickly. Water and milk are the everyday drinks that protect teeth rather than threaten them. Reserving sweet drinks for mealtimes, using a straw, and following them with water are simple swaps that meaningfully lower a child's cavity risk without feeling like deprivation.

Prevention is a partnership between what happens at home and what happens at the dental office. Build the daily habits, watch the snacking and the bedtime bottle, and keep the checkups, and you give your child an excellent chance of growing up cavity free. Few health investments are as simple, or as lasting, as teaching a child to care for their teeth from the very beginning.

Read more…

A knocked-out tooth or sudden severe pain is frightening, but quick, informed action can change the outcome.

Emergency-Dental.jpg

Dental emergencies have a way of happening at the worst possible time, on a weekend, during a game, or in the middle of the night. In those moments, knowing what to do in the first few minutes can mean the difference between saving and losing a tooth. A little preparation goes a long way.

A knocked-out tooth is a race against the clock

If a permanent tooth is knocked out, time matters enormously. Pick the tooth up by the crown, the part you normally see, never by the root. If it is dirty, rinse it gently with water without scrubbing. If you can, place it back in the socket and hold it there. If that is not possible, tuck it inside your cheek or put it in a container of milk, which keeps the delicate root cells alive far better than water. Then get to a dentist immediately. A tooth reimplanted within about 30 minutes to an hour has the best chance of surviving.

For a tooth that is cracked or broken, rinse your mouth with warm water and apply a cold compress to the outside of the face to control swelling. Save any pieces if you can. Prompt care gives the best chance of repair.

Pain, swelling, and other urgent situations

Severe, persistent toothache, especially with swelling, can indicate an infection that needs prompt treatment. Rinse with warm salt water, use a cold compress, and take an over-the-counter pain reliever as directed, but do not place aspirin directly on the gum, which can burn the tissue. Facial swelling, particularly if it affects your eye or throat or comes with fever, is serious and should be treated urgently. A lost filling or crown, while less dramatic, still deserves a timely call to prevent further damage.

For everyday injuries like a bitten lip or tongue, clean the area gently and use a cold compress. Bleeding that will not stop after direct pressure is a reason to seek care right away.

The best time to prepare for an emergency is before one happens. Knowing a local dentist you can call, and saving their number in your phone, means you are not searching desperately for help while a tooth's survival depends on the clock.

Preventing emergencies in the first place

Many dental emergencies are avoidable with a little foresight. If you or your child play contact sports, a properly fitted mouthguard is one of the best investments you can make, since it protects against exactly the kind of impact that knocks out or fractures teeth. Avoiding habits like chewing ice, opening packages with your teeth, or biting hard candies prevents a surprising number of cracked teeth.

Routine care is preventive too. Regular checkups catch weakened teeth, loose fillings, and brewing infections before they fail at an inconvenient moment. A tooth that breaks over a holiday weekend was often showing warning signs at a checkup that never happened. Staying current with dental visits, and addressing small problems promptly, quietly removes many of the situations that would otherwise become emergencies.

Children's emergencies deserve a special note. If a baby tooth is knocked out, do not try to put it back, since forcing it into the socket can damage the developing permanent tooth underneath. Instead, control any bleeding and call the dentist for guidance. For a knocked-out permanent tooth in an older child, the same fast action that applies to adults gives the best chance of saving it. When in doubt with a child, a quick phone call to the dental office is always the safest first move.

Most dental emergencies are far more manageable when you stay calm and act quickly. Keep a small dental first-aid kit with gauze, a container, and your dentist's contact information, and make sure your family knows the basics. In an emergency, those first few minutes are precious, and knowing how to use them is often what saves the smile.

Read more…

If the thought of the dentist makes your stomach tighten, you are far from alone, and modern care has answers.

dental-anxiety.jpg

Fear of the dentist is one of the most common anxieties there is. Surveys suggest a large share of adults feel some degree of nervousness about dental visits, and a meaningful number avoid care entirely because of it. If that describes you, the first thing to know is that this is a recognized, understood experience, and that the profession has spent years learning how to address it.

Where the fear comes from

Dental anxiety has many roots. For some, it traces back to an uncomfortable experience years ago, often in childhood when procedures were less gentle than they are today. For others, it is the loss of control of lying back while someone works in your mouth, the sounds and sensations, or a fear of pain or of being judged for the condition of their teeth. All of these are valid, and none of them are unusual.

The trouble is that avoidance feeds the cycle. Skipping visits allows small problems to grow into bigger ones, which eventually require more involved treatment, which confirms the original fear. Breaking that loop early, while care is still simple, is the kindest thing you can do for yourself.

What actually helps

Modern dentistry has changed dramatically. Techniques are gentler, numbing is more effective, and offices are increasingly designed with comfort in mind. The single most powerful tool, though, is communication. Telling your dentist that you feel anxious is not awkward, it is useful. It lets them slow down, explain each step before it happens, and agree on a signal you can raise if you need a break. That sense of control alone eases many people's fear.

Other strategies help too. Scheduling morning appointments so the visit does not loom over your day, bringing headphones and music, practicing slow breathing, and starting with a simple cleaning rather than a big procedure all build confidence gradually. For stronger anxiety, sedation options ranging from laughing gas to other calming medications can make treatment comfortable and even hazy in memory.

The key is finding a provider who takes your comfort seriously. A compassionate dentist who listens without judgment and works at your pace can genuinely change your relationship with dental care, turning something you dread into something manageable.

Helping an anxious child, and rebuilding your own trust

Anxiety often takes root in childhood, so how a child experiences early visits shapes their attitude for years. Keeping your language calm and positive, avoiding scary words, and choosing a practice that is patient and gentle all help a nervous child feel safe. Children also take their cues from parents, so managing your own visible worry does more than you might expect.

For adults who have avoided care for a long time, rebuilding trust works best in small steps. Start with a simple, low-pressure appointment like a consultation or a basic cleaning rather than committing to a large procedure right away. Each calm, pain-free visit chips away at the fear and replaces it with evidence that things have changed. Progress does not have to be dramatic. A series of manageable visits gradually turns dread into routine, and that shift is entirely achievable with the right provider and a bit of patience.

It also helps to understand the sedation options, since fear of pain drives so much dental anxiety. The mildest is nitrous oxide, or laughing gas, which wears off within minutes and lets you drive yourself home. For deeper anxiety, dentists can offer oral sedation that leaves you calm and drowsy, or, for extensive procedures, stronger options administered under careful monitoring. Having these tools available means that even significant fear does not have to stand between you and the care you need.

You do not have to white-knuckle your way through, and you certainly do not have to keep avoiding care and hoping problems disappear. Anxiety is a reason to choose the right dentist and to speak up, not a reason to stay away. With the right approach, even lifelong dental fear can soften into something you can handle, one comfortable visit at a time.

Read more…

Knowing what a routine visit involves takes the mystery out of it, and knowing the red flags could save a tooth.

advkulq.webp

For something so routine, a dental checkup is often misunderstood. Some people expect only a cleaning, others dread a lecture, and many are not sure what the dentist is actually looking for. Demystifying the visit makes it far less stressful, and understanding the warning signs between visits is just as valuable.

The anatomy of a routine visit

A typical checkup has two parts: the exam and the cleaning. During the exam, the dentist inspects each tooth for decay, checks the condition of existing fillings and crowns, and evaluates your gums for signs of disease by measuring how snugly they hug the teeth. Most exams include an oral cancer screening, a quick but important look at the soft tissues of the mouth, tongue, and throat. Periodic x-rays reveal decay and other issues hidden between teeth or below the gumline.

The cleaning that follows removes plaque and hardened tartar that brushing cannot, polishes the teeth, and often finishes with fluoride to strengthen enamel. The whole appointment usually takes under an hour, and for a healthy mouth it is painless. Along the way you can ask questions about anything, from a sensitive spot to whitening options.

Signs that warrant a call before your next visit

Checkups are preventive, but some symptoms should not wait for the calendar. Gums that bleed regularly when you brush are a sign of inflammation that deserves attention. Persistent bad breath or a bad taste can signal infection. Tooth sensitivity to hot or cold that lingers, a dull ache, or sharp pain when biting can all point to decay or a cracked tooth. A sore, lump, or patch in the mouth that does not heal within two weeks should always be checked.

Swelling in the face or gums, especially with pain or fever, is closer to an emergency and should prompt a prompt call. Dental infections do not resolve on their own, and ignoring them can allow the problem to spread. The general rule is simple: pain and swelling are your body asking for help, not something to push through.

Whether you are due for a routine visit or noticing one of these warning signs, the solution starts with establishing care. Finding a Dentist near me that you trust means you have someone to call the moment something feels off, rather than scrambling to find a provider during a painful weekend.

How often should you actually go

For most healthy adults, a checkup and cleaning every six months is the standard, and it works well because it matches the pace at which plaque, tartar, and early decay tend to accumulate. Some people benefit from more frequent visits, including those with a history of gum disease, smokers, diabetics, and anyone prone to cavities. Your dentist will recommend an interval based on your own risk rather than a one-size-fits-all rule.

Children need regular visits too, generally starting by their first birthday and continuing every six months as their teeth develop. Consistency at every age is the point. Skipping visits for years and returning only when something hurts almost always means a bigger, costlier problem than the routine care would have prevented. The rhythm of regular appointments is what keeps small issues from ever becoming large ones.

A common worry about checkups is dental x-rays, so it is worth putting in perspective. Modern digital x-rays use very low doses of radiation, far less than older film, and dentists take them only at appropriate intervals based on your needs. They are one of the most valuable diagnostic tools available, revealing decay between teeth, problems below the gumline, and issues with the roots and bone that no visual exam can catch. Used sensibly, their benefit in catching hidden problems early far outweighs the minimal exposure.

A checkup is not something to fear or to skip. It is a short, straightforward appointment that keeps small problems small. Pair those regular visits with a habit of paying attention to changes in your mouth, and you give yourself the best possible odds of keeping every tooth healthy for life.

Read more…

Those first tiny teeth are temporary, but the habits and health built around them last a lifetime.

Why-Baby-Teeth-Matter-More-Than-You-Think-scaled.jpg

It surprises many new parents to learn that a child should see a dentist by their first birthday, or within six months of the first tooth appearing. A single tooth hardly seems to warrant an appointment. But that first visit is less about the tooth and more about setting the stage for a lifetime of healthy habits, and about catching trouble before it starts.

Baby teeth do real work

It is tempting to think of baby teeth as disposable placeholders. They are far more than that. Primary teeth help a child chew and eat properly during years of rapid growth. They shape clear speech as a child learns to talk. And critically, they hold space in the jaw for the permanent teeth developing underneath. When a baby tooth is lost too early to decay, neighboring teeth can drift into the gap, crowding out the adult tooth that was meant to take its place and setting up orthodontic problems years later.

Tooth decay is the most common chronic disease of childhood, more common than asthma. And it can begin as soon as teeth appear, especially when a baby falls asleep with a bottle of milk or juice. The sugars pool around the teeth overnight and feed the bacteria that cause cavities. Early dental visits are the first line of defense against this.

What the early visits look like

A first appointment is gentle and short. The dentist checks the erupting teeth and gums, looks at how the jaw is developing, and, just as importantly, coaches parents. You will learn how to clean an infant's teeth, how much fluoride toothpaste is appropriate, how diet affects decay, and how to ease a child through teething. For toddlers, these regular visits build familiarity, so the dental office becomes a normal, unthreatening place rather than something to fear.

A practice that focuses on children is built for exactly this. The pace, the language, the tools, and the atmosphere are all designed to keep a young child calm and cooperative, which makes each visit easier than the last.

Establishing care with a pediatric dentist early gives your child a dental home, a consistent provider who tracks their development over time and knows their history. That continuity pays off, because small issues get spotted and addressed before they become painful or expensive.

Making dental visits a positive experience

A child's early feelings about the dentist tend to stick, so it is worth being intentional. Keep your own language upbeat and neutral, and avoid words like hurt, shot, or pain, even in reassurance, since those can plant an idea that was not there before. Reading books about visiting the dentist or playing pretend at home helps a young child know what to expect and feel in control.

Timing matters too. Schedule appointments when your child is well rested rather than tired or hungry, and try to stay calm yourself, because children read a parent's anxiety instantly. A practice that specializes in young patients will have its own gentle ways of explaining tools and building trust, turning the visit into something closer to an adventure than an ordeal. Each positive experience makes the next one easier.

It also helps to know what is normal along the way. Teething can make an infant fussy and eager to chew, and a clean, chilled teething ring usually offers relief. As baby teeth give way to permanent ones, some wiggling and gaps are expected. When you are unsure whether something is routine or worth a closer look, a quick call to your child's dental office is always better than worrying, and it is exactly the kind of guidance a dedicated children's practice is happy to provide.

The simplest way to protect your child's smile is to start early and stay consistent. Clean those first teeth twice a day, watch the bedtime bottle, keep sugary drinks to a minimum, and keep the regular checkups. A healthy start with baby teeth is one of the best investments you can make in the permanent smile that follows.

Read more…

More adults are choosing orthodontic treatment than ever before, and the reasons go well beyond appearance.

2615253.jpg

There is a persistent myth that orthodontic treatment belongs to middle school, and that once you are an adult the window has closed. It has not. Teeth can be moved at almost any age, because the biological process that lets them shift, the steady remodeling of the bone that holds each root in place, continues throughout life. Today roughly one in four orthodontic patients is an adult, and the number keeps climbing.

Why adults are seeking treatment

Some adults never had the chance to fix their teeth as children. Others had braces years ago, skipped wearing their retainer, and watched their teeth gradually drift back. And many are motivated by something more than looks. Crooked or crowded teeth are harder to clean, which raises the risk of cavities and gum disease. A misaligned bite can wear enamel unevenly, strain the jaw joint, and even contribute to headaches. Straightening the teeth is often as much about long-term health as it is about a better smile.

There is also a confidence factor that is hard to overstate. Adults frequently describe holding back a smile in photos or meetings for years. Correcting that can change how a person carries themselves in ways that ripple through their professional and social life.

The options have come a long way

The image of a mouth full of bulky metal brackets no longer reflects modern treatment. Adults today can often choose from clear or tooth-colored braces, clear aligner systems that are nearly invisible, and appliances that are far more comfortable than the versions their parents wore. The right choice depends on the complexity of the case, and that is a conversation best had with a specialist who can weigh the trade-offs for your specific bite.

Adult treatment does have a few differences worth knowing. Because adult bone is fully mature, some movements take a little longer than they would in a growing child, and existing dental work like crowns, bridges, or gum recession needs to be factored into the plan. None of these are barriers. They simply make it more important to work with an experienced provider who plans around them from the start.

The first step is straightforward. A consultation with an orthodontist will typically include images or a digital scan of your teeth, a discussion of your goals, and a realistic overview of your options, timeline, and cost. Many practices offer this initial visit at no charge, so there is little downside to simply finding out where you stand.

What to expect from the process

Adult treatment timelines vary with the complexity of the case, but many run somewhere between a year and two and a half years, and simpler corrections can finish faster. Throughout, you will have periodic appointments to adjust braces or check aligner progress, spaced a few weeks apart. Modern treatment is designed to fit around a working life, and clear options in particular let most people move through it without anyone noticing.

One step adults should take seriously is retention. Teeth have a natural tendency to drift back toward their old positions, which is exactly how many adults ended up needing treatment a second time. Wearing a retainer as directed after the braces or aligners come off is what locks in the result for good. It is a small, ongoing habit, and it protects everything the treatment accomplished.

Cost and insurance are worth raising early, because they often turn out to be less of an obstacle than people assume. Many dental plans include some orthodontic benefit even for adults, and most practices offer monthly payment options that spread the investment over the length of treatment. A consultation is the right place to get real numbers for your case rather than guessing, and it costs you nothing to find out where you stand.

Whatever brought you to the idea, whether a health concern, a wedding on the calendar, or simply a lifelong wish to fix something that has always bothered you, the takeaway is the same. Age is not the obstacle it is made out to be. With modern methods and a good specialist, adults can achieve the same healthy, well-aligned results as anyone else, often more comfortably and more discreetly than they expect.

Read more…