All Posts (5122)

Sort by

Bowling-Green-Orthodontist-881x587.jpg

If you have ever wondered what goes on behind the scenes after your first orthodontic consultation, you are not alone. Most patients walk out of that initial appointment knowing they need treatment, but feeling a bit uncertain about what comes next. I get it. There is a gap between "yes, you need braces" and actually getting them placed, and that gap can feel mysterious. Let me walk you through exactly what happens during that time, because understanding the process can make the whole experience feel less intimidating.

Your First Appointment Is More Than a Quick Look

What happens at your first orthodontist appointment is actually quite involved, even if it feels brief from your perspective. When you sit in my chair for the first time, I am doing far more than glancing at your teeth to see if they are crooked. I am evaluating your entire oral system: how your jaws relate to each other, how your teeth fit together when you bite, whether there are any airway concerns, and how your facial profile balances overall.

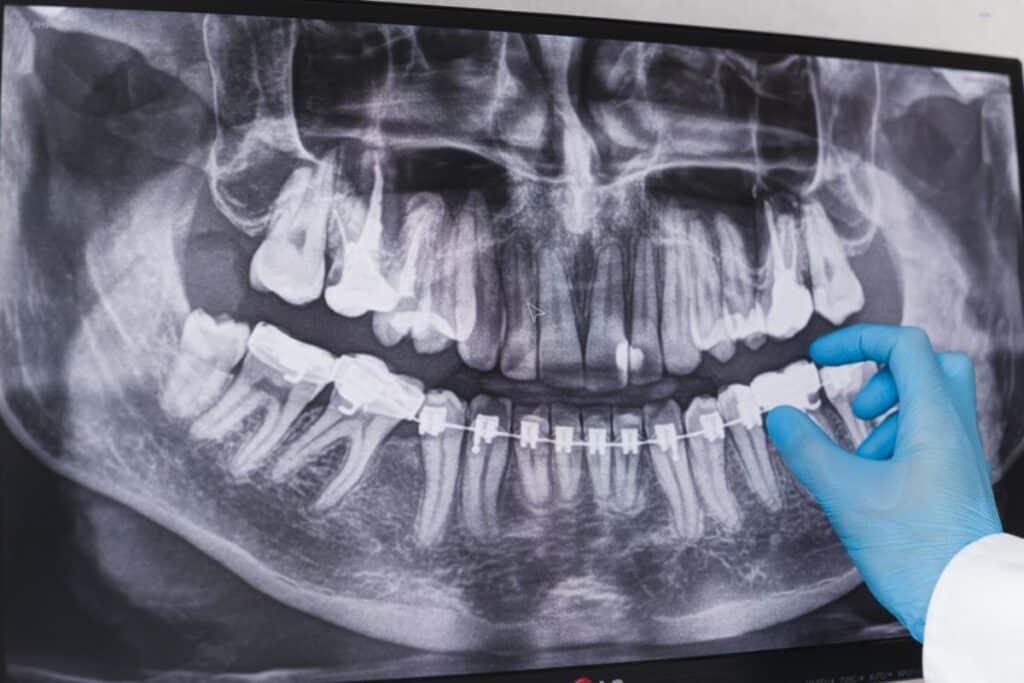
During that first visit, we typically take a series of diagnostic records. These usually include digital X-rays, including a panoramic image that shows all your teeth and jaw structures, plus a cephalometric X-ray that gives us a side profile view of your skull. We also take photographs of your face and teeth from multiple angles, and in many offices today, we use an intraoral scanner to create a precise three-dimensional digital model of your teeth. Gone are the days when everyone had to bite into trays of goopy impression material, though some offices still use traditional impressions for certain situations.

I also spend time during that first visit simply talking with you. What bothers you about your smile? Are you experiencing jaw pain or headaches? Do you have trouble chewing? Your concerns and goals matter enormously in shaping the treatment plan, because orthodontics is not one-size-fits-all.

The Diagnostic Process Behind the Scenes

After your first appointment ends, my work is really just beginning. This is the part patients rarely see, but it is where the most critical thinking happens. I sit down with all those records and begin a thorough analysis. The cephalometric X-ray gets traced, either digitally or by hand, to measure the angles and relationships between your upper jaw, lower jaw, and skull base. These measurements tell me whether a bite problem is caused by tooth position, jaw position, or some combination of both.

I study the panoramic X-ray to check for missing teeth, extra teeth, root issues, or any pathology that might affect treatment. I examine how much bone surrounds each tooth, because that influences how and where we can safely move things. For younger patients, I look at growth potential, estimating how much jaw growth remains and whether we can use that growth to our advantage.

The digital models or scans let me measure crowding or spacing down to the millimeter. I can see exactly how much room we need to create, or how much excess space needs to be closed. I analyze your bite from every angle: front, back, left side, right side. Every single detail matters when the goal is a result that looks great, functions perfectly, and stays stable long term.

How the Treatment Plan Takes Shape

So how do orthodontists decide on a treatment plan? It is a process of weighing all the diagnostic information against your specific goals and circumstances. There is rarely just one way to fix a problem; there are usually several approaches, each with different trade-offs regarding treatment time, aesthetics during treatment, cost, and long-term stability.

For example, a patient with moderate crowding might be treated by expanding the arch, by removing two or four teeth to create space, or by slimming the teeth slightly between contacts. Each approach has pros and cons, and the best choice depends on factors like facial profile, lip position, gum health, and patient preference. I have seen cases where two equally qualified orthodontists might choose different paths for the same patient, and both could achieve excellent results.

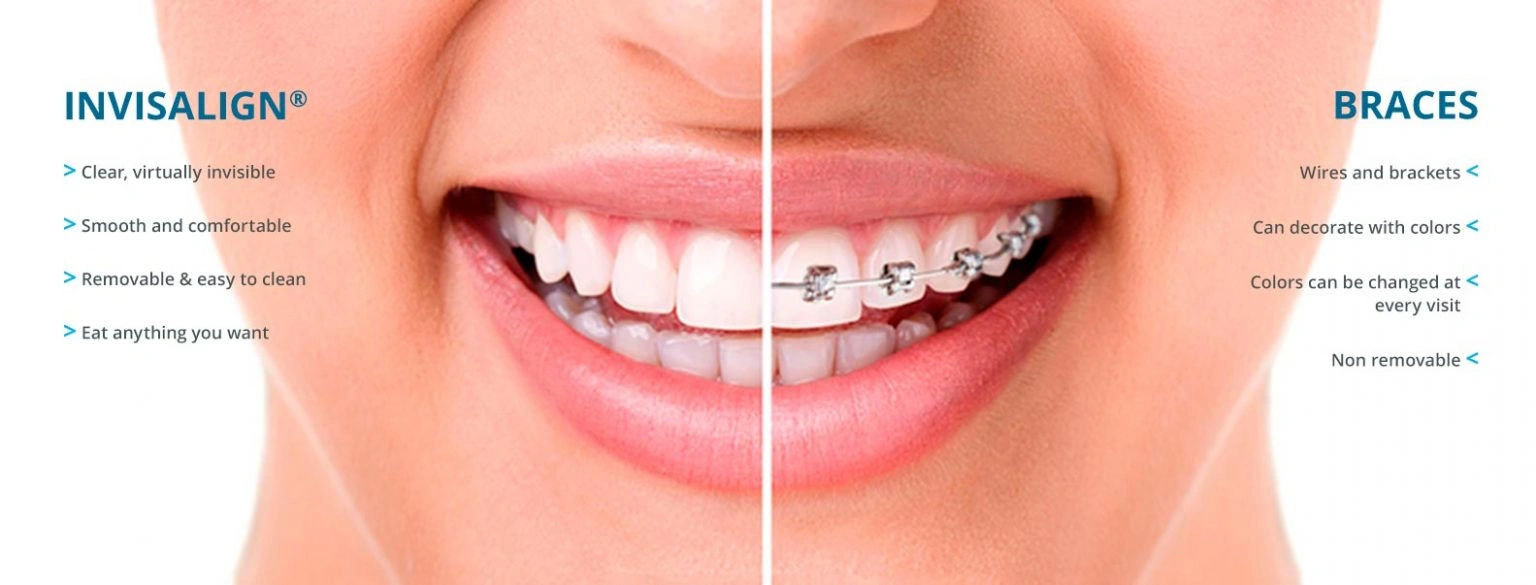
I also consider the appliance options. Traditional metal braces, ceramic braces, lingual braces placed behind the teeth, and clear aligners are all tools in our toolbox. Not every tool works for every situation. Severe bite problems might require braces for optimal control, while mild crowding in an adult might be beautifully managed with aligners. Part of my job is matching the right tool to the right problem.

When Additional Steps Are Needed First

Sometimes the treatment plan involves steps that must happen before orthodontic appliances go on. A patient with active gum disease needs that managed first, because moving teeth through inflamed tissue is like building a house on a shaky foundation. Someone with a cavity needs that filled. An impacted canine might require a minor surgical procedure to expose it so we can guide it into position.

For growing patients, we might recommend a phase of early treatment to correct a jaw discrepancy before comprehensive braces later. I recently had a nine-year-old patient whose lower jaw was growing ahead of the upper jaw, creating a crossbite. We addressed that with a palatal expander first, then waited for more permanent teeth to come in before starting full braces. Timing matters in orthodontics, and sometimes waiting is actually the most strategic choice.

The Presentation Appointment

Once I have completed the analysis and designed a plan, you come back for what we often call the consultation or case presentation appointment. This is where I walk you through everything: what the problems are, how I propose to fix them, how long treatment will likely take, and what it will cost. I show you your X-rays and photos, explain what I see, and make sure you understand why I am recommending what I am recommending.

This appointment is your opportunity to ask every question on your mind. How often will I need to come in for adjustments? Will I need rubber bands? Will it hurt? What happens if I choose not to treat? Good orthodontists welcome these questions because informed patients make better partners in their own care. I would rather spend an extra twenty minutes answering questions than have a patient feel uncertain or rushed.

Getting Started With Treatment

After you have agreed to the plan and handled the financial arrangements, we schedule your bonding appointment or your first aligner delivery. Depending on the office and the complexity of your case, this might be a week later or a month later. Some treatments require lab work, custom appliances to be fabricated, or aligners to be manufactured, all of which take time.

The day you actually get your braces on or pick up your first set of aligners, the treatment plan that took weeks of careful analysis and planning finally becomes visible. But all that invisible work is what makes the visible result possible. Every bracket is placed at a specific angle and height, calculated to move each tooth to its ideal position. Every wire is selected for its specific properties. Nothing is random.

I share all of this because I want patients to understand that orthodontic treatment planning is genuinely complex. It requires years of specialty training beyond dental school, and it involves a level of analysis that goes far beyond what meets the eye. When there is a gap between your first visit and the start of treatment, that time is being used wisely. Your orthodontist is crafting a plan designed specifically for you, and that careful planning is what makes excellent results possible.

Read more…

main-dentalcheckupimportance.jpg

I had a patient come in last year who had not seen a dentist in about seven years. He was in his early 40s, generally healthy, and had avoided dental care not because of fear or financial hardship, but simply because nothing seemed wrong. His teeth did not hurt. He brushed every day. He figured he was fine. By the time he showed up in my office, he had three teeth that needed crowns, two that needed root canals, and one that was beyond saving entirely. His treatment plan totaled several thousand dollars and required months of appointments. The thing that struck me most was his genuine shock. He had no idea so much could go wrong while feeling perfectly normal.

Why Dental Problems Are Silent

What happens if you do not go to the dentist for years? The short answer is that problems develop, progress, and compound, often without any symptoms at all. This is the fundamental challenge of dental health that many people do not grasp intuitively. This is also why pediatric dentists are so important. Unlike a sprained ankle or a sore throat, most dental diseases are painless in their early and middle stages. A cavity does not hurt until it reaches the nerve of the tooth. Gum disease does not cause discomfort until it has already destroyed significant bone support. By the time you feel something, the problem has usually been developing for months or years.

This is fundamentally different from most health issues people are familiar with. We are conditioned to think that our body will alert us when something is wrong. For dental problems, that alert system is delayed so significantly that by the time it activates, the problem has often escalated from simple to complex, from inexpensive to costly, from fixable to potentially irreversible.

The Progression of Untreated Decay

Let me walk you through a typical progression. A small area of decay begins where bacteria have penetrated the enamel, usually between teeth or in the grooves of a molar. At this stage, the cavity is tiny. Treating it takes about fifteen minutes and involves removing a minimal amount of tooth structure and placing a small filling. You feel nothing because the decay is nowhere near the nerve. Cost is modest. Discomfort during treatment is essentially zero.

Skip your checkup, and that cavity grows. Within a year or two, it has expanded into the dentin layer beneath the enamel, which is softer and decays faster. The filling needed now is larger. Still no pain, but more tooth structure is lost. Give it another year or two without treatment, and the decay approaches the nerve. At this point you might start experiencing sensitivity to cold or sweets, but many people dismiss these as normal. The filling option is no longer on the table; now we are talking about a crown to restore the weakened tooth structure, or a root canal if the nerve becomes infected.

Wait even longer and the infection can spread to the bone at the tip of the root, forming an abscess. Now you have pain, swelling, and possibly a systemic infection requiring antibiotics. The tooth may still be saveable with a root canal and crown, or it may be so compromised that extraction is the only option. Replacing an extracted tooth with an implant costs considerably more than any of the earlier interventions would have.

Gum Disease: The Other Silent Threat

Tooth decay gets most of the attention, but periodontal disease is actually the leading cause of tooth loss in adults. It begins as gingivitis, a reversible inflammation of the gums caused by bacterial plaque accumulation. You might notice some bleeding when you brush or floss, but it does not hurt and many people ignore it. Professional cleanings at regular intervals prevent gingivitis from progressing.

Without those cleanings, gingivitis can advance to periodontitis, where the infection moves below the gum line and begins destroying the bone that holds teeth in place. This bone loss is irreversible. It does not grow back. As the bone recedes, teeth gradually loosen. Pockets form between the gums and teeth, harboring more bacteria and accelerating the destruction. Advanced periodontitis can lead to multiple tooth loss, and the treatment to manage it involves deep cleaning procedures, possible surgery, and lifelong maintenance appointments every three to four months.

How Often Should You Really See a Dentist

How often should you really see a dentist? For most people, the traditional recommendation of every six months remains sound. This interval allows us to catch decay early, monitor gum health, and remove calculus buildup before it causes problems. However, some patients benefit from more frequent visits. If you have active gum disease, a history of frequent cavities, diabetes, or a compromised immune system, visits every three to four months may be appropriate.

Conversely, a patient with consistently excellent oral health, no history of decay, healthy gums, and good home care might be fine stretching to annual visits. The key is that the interval should be determined by your individual risk factors and discussed with your dentist, not arbitrarily decided based on how your teeth feel at any given moment.

The Financial Reality

The irony of skipping dental visits to save money is that it almost always costs more in the long run. A routine exam and cleaning twice a year is a predictable, manageable expense. The emergency root canal at two in the morning, the crown that follows, the implant to replace the tooth that could not be saved: these are the expenses that strain budgets and create financial stress. Preventive care is not just medically superior; it is financially superior by a wide margin.

I understand that dental care has real costs and that not everyone has insurance or flexible spending accounts. But even patients with limited budgets benefit from prioritizing preventive visits. Many practices offer payment plans, sliding scale fees, or in-house savings programs. Dental schools provide quality care at reduced rates. Community health centers offer services on an income-based scale. The options exist if you seek them out.

What Happens at That Comeback Visit

If you have been away for years and you are reading this with some apprehension, let me tell you what to expect. We will take comprehensive radiographs to see what is happening in areas we cannot examine visually. We will do a thorough clinical exam. We will measure your gum health. And then we will sit down and talk about what we find. If treatment is needed, it will be prioritized. We address urgent issues first, then work through remaining needs at a pace that works for you clinically and financially.

I never expect a patient who has been away for seven years to complete all their treatment in one visit. We develop a plan, we tackle it in stages, and we get your mouth to a healthy baseline from which preventive care can do its job. The first step is simply showing up. What follows is always manageable when approached systematically.

Your teeth are non renewable resources. You get one set of adult teeth, and they need to last the rest of your life. The maintenance required to keep them healthy is minimal compared to the intervention required to repair or replace them once they fail. Those routine visits are not just appointments; they are investments in your future comfort, health, and financial wellbeing. If it has been a while, this is your reminder that the best time to go back is now, before the small problems you cannot feel become big problems you cannot ignore.

Read more…

what-does-an-invisalign-do-20260322050258.webp

For many people, Invisalign feels like the modern answer to traditional braces. The clear trays look simple, removable, and far less noticeable than metal brackets. Because of this, many patients begin treatment expecting an easy experience with very few challenges. What often gets overlooked, however, is that Invisalign still requires daily discipline and careful maintenance to work properly. The growing popularity of clear aligners has also created unrealistic expectations online. Short videos and smile transformation posts usually focus on final results instead of the responsibilities involved during treatment. Some patients are surprised to discover that Invisalign can become frustrating when aligners are not worn correctly or when treatment goals are more complex than expected. During conversations about long-term oral development, a pediatric dentist in Cumming may also explain to parents that removable aligners are not always the perfect solution for every child or teenager, especially when growth-related dental concerns are involved.

Key Takeaways

  • Invisalign offers flexibility, but requires strong daily commitment.
  • Some orthodontic problems respond better to braces.
  • Aligners must stay in place most of the day.
  • Poor habits can slow or weaken treatment progress.
  • Oral hygiene still plays a major role during Invisalign treatment.

Invisalign Depends on Self-Discipline

One hidden challenge with Invisalign is personal responsibility. Braces continue working all day because they stay attached to the teeth. Invisalign only works when patients wear the trays consistently. Most treatment plans require aligners to stay in the mouth for about 22 hours daily. Removing them too often can interrupt tooth movement and extend treatment time. Many patients struggle with consistency during social events, vacations, school schedules, or busy workdays. Even small breaks from the routine may affect results over time.

Removing Aligners Sounds Easier Than It Feels

At first, removable trays sound convenient. Patients can eat freely and brush normally without wires getting in the way. But over time, constant removal becomes tiring for some people. Every snack or drink other than water usually requires removing the aligners first. After eating, teeth should ideally be cleaned before placing the trays back in the mouth. Some patients begin skipping snacks or delaying meals simply because managing aligners feels inconvenient during the day.

Invisalign Is Not Completely Invisible

Many advertisements describe Invisalign as nearly invisible. While the trays are clear, some treatment plans require additional attachments bonded to the teeth. These small tooth-colored bumps help guide difficult tooth movements more effectively. Although subtle, they may still become noticeable during close conversations or photos. Certain patients may also need rubber bands or other orthodontic tools alongside their aligners, making treatment more visible than expected.

Complex Cases May Need Traditional Braces

Invisalign works well for many mild and moderate alignment concerns. However, not every orthodontic issue responds equally well to removable trays. Severe crowding, large bite problems, major tooth rotations, or complicated jaw concerns sometimes require traditional braces for better control. Some patients even need a combination of braces and aligners during different treatment phases. This is why proper consultation matters before choosing a treatment option based only on appearance or marketing trends.

Aligners Can Easily Get Lost or Damaged

Because Invisalign trays are removable, losing them is surprisingly common. Patients often wrap aligners in tissues during meals and accidentally throw them away. Heat exposure can also damage the plastic. Leaving trays inside a hot car or rinsing them with hot water may warp their shape. Damaged aligners may no longer fit correctly, which can affect tooth movement and delay progress.

Speech Changes Sometimes Happen

Some patients notice small speech differences when they first begin wearing aligners. Certain words may sound different during the adjustment period. This temporary lisp usually improves as the mouth adapts to the trays. However, people who speak frequently at work or school may initially feel self-conscious. The adjustment period varies from person to person.

Oral Hygiene Still Requires Attention

One common misconception is that Invisalign automatically creates a cleaner orthodontic experience than braces. While brushing and flossing may feel easier, oral hygiene still requires effort. Food particles trapped beneath aligners can stay against the teeth for long periods. This may increase the risk of plaque buildup, cavities, or gum irritation if cleaning habits are poor. Patients should clean both their teeth and aligners regularly to maintain healthy treatment conditions.

Treatment Delays Are More Common Than Expected

Many Invisalign treatment plans are based on ideal patient cooperation. When aligners are not worn properly, teeth may stop tracking according to the original plan. This sometimes leads to additional aligners, refinement stages, or longer treatment periods than expected. Patients who frequently forget trays or skip wear time often experience slower progress.

Convenience Can Create Carelessness

Ironically, the convenience of removable aligners sometimes creates bad habits. Because trays can be removed anytime, some patients become less consistent over time. Traditional braces do not offer that flexibility, which means they continue working continuously without depending on daily decisions. For motivated and disciplined patients, Invisalign can produce excellent results. But patients who struggle with routines may find treatment more difficult than expected.

Understanding the Full Picture before Treatment

Invisalign has transformed orthodontic care for many people. The system offers comfort, flexibility, and a more discreet appearance compared to traditional braces. Still, successful treatment depends on much more than simply receiving clear trays. Consistency, hygiene, responsibility, and realistic expectations all play major roles in achieving good results. In some cases, a pediatric dentist may also help younger patients and parents understand whether clear aligners are suitable based on oral development, habits, and long-term dental needs. Patients who understand both the benefits and the limitations before starting treatment are often better prepared for the process ahead.

Read more…

retainers-20260215003745.webp

Finishing braces or clear aligner treatment often feels like the final step in the journey toward a straighter smile. Many people expect their teeth to stay perfectly aligned forever once treatment ends. But teeth naturally shift over time. Without proper retention, even beautifully aligned teeth can slowly move back into old positions.

This is where removable clear retainers become important. These transparent devices are designed to hold teeth in place after orthodontic treatment. They may look simple, but they play a major role in protecting months or even years of dental correction.

Many patients are surprised to learn that retention is considered one of the most important phases of orthodontic care. In fact, an experienced orthodontist in Houston may spend just as much attention on long-term retention planning as the alignment process itself because maintaining results is just as important as creating them.

Key Takeaways

  • Teeth can shift naturally after braces or aligners.
  • Clear retainers help maintain smile alignment.
  • Retainers are removable and nearly invisible.
  • Daily care helps retainers last longer.
  • Skipping retainer use may reverse treatment progress.

What Are Removable Clear Retainers?

Removable clear retainers are custom-made trays that fit over the teeth. They are usually made from transparent plastic material and are designed to keep teeth stable after orthodontic treatment. Unlike braces, retainers do not move teeth aggressively. Their main purpose is to prevent unwanted shifting while the surrounding bone and tissues stabilize.

Because they are clear and lightweight, many patients prefer them over traditional wire retainers.

Why Teeth Move After Treatment

Many people think teeth become permanently fixed after braces come off. In reality, teeth remain capable of movement throughout life.

Several factors can contribute to shifting, including:

  • Natural aging
  • Jaw growth
  • Teeth grinding
  • Pressure from chewing
  • Previous alignment problems

After orthodontic treatment, the surrounding tissues need time to adapt to the new tooth positions. Retainers help guide this transition and reduce the risk of relapse. Without retention, teeth may gradually crowd, rotate, or drift out of alignment again.

Benefits of Clear Retainers

Clear retainers have become popular because they offer both comfort and convenience.

Nearly Invisible Appearance

One major advantage is their discreet appearance. Since the trays are transparent, most people barely notice them during conversations or social situations.

Easy Removal

Patients can remove retainers while eating, brushing, and flossing. This makes oral hygiene much easier compared to fixed appliances.

Comfortable Fit

Custom retainers are molded to fit each patient’s teeth closely. Most people adjust to wearing them quickly.

Protection against Minor Shifting

Retainers help maintain the hard work completed during orthodontic treatment. Consistent wear keeps teeth stable and aligned.

How Often Should Retainers Be Worn?

Wear schedules vary depending on the patient and treatment history. Many orthodontic patients are asked to wear retainers full-time at first. After the stabilization period, some patients transition to nighttime-only wear. The most important factor is consistency. Missing several days or weeks of retainer use may allow teeth to shift enough to create fitting problems. If a retainer suddenly feels tight, it may be a sign that teeth have already started moving slightly.

Cleaning and Caring for Retainers

Proper cleaning keeps retainers clear, fresh, and safe to wear. Dirty retainers can collect bacteria, plaque, and odors over time.

Helpful cleaning habits include:

  • Rinsing retainers after removal
  • Brushing gently with a soft toothbrush
  • Using mild soap or approved cleaner
  • Avoiding hot water that may warp plastic
  • Storing retainers in a protective case

Many patients accidentally damage retainers by wrapping them in napkins during meals. Pets are also known for chewing retainers left unattended. Simple care habits can extend the life of the appliance significantly.

Common Mistakes Patients Make

One common mistake is assuming retainers are optional after a few months. Some people stop wearing them once their teeth appear stable. Unfortunately, tooth movement can happen slowly and quietly over time. Small changes may become noticeable only after alignment has already shifted. Another mistake is failing to replace damaged retainers promptly. Cracked or loose retainers may not hold teeth correctly. Patients should also avoid exposing retainers to heat inside cars or dishwashers, as high temperatures can distort their shape.

Clear Retainers vs. Permanent Retainers

Some patients receive fixed retainers attached behind the teeth, while others use removable retainers. Each option has advantages. Removable retainers are easier to clean and less noticeable during daily oral hygiene. However, they depend on patient discipline. Permanent retainers stay attached continuously, but cleaning around them may require extra effort. Orthodontic recommendations usually depend on individual bite patterns and long-term stability needs.

Protecting Your Smile for the Future

Orthodontic treatment is a major investment of time, effort, and patience. Retainers help protect that investment long after braces or aligners are removed.

Wearing a retainer may feel like a small step, but it plays a powerful role in preserving alignment and preventing future correction needs.

A straight smile is not only created during treatment. It is maintained through consistent care afterward. By following retainer instructions and practicing good oral habits, patients can enjoy stable and confident smiles for many years ahead.

Read more…

13676200099?profile=RESIZE_710x

I want to start by saying something that might seem obvious but rarely gets stated plainly: if going to the dentist makes you anxious, you are not weak, you are not being dramatic, and you are absolutely not alone. Dental anxiety affects somewhere between 30 and 40 percent of the adult population, depending on which study you reference. For roughly 10 to 15 percent of people, the fear is severe enough that they avoid dental care entirely, sometimes for years or even decades. I see the consequences of that avoidance regularly, and I also see how much relief patients feel when they discover that modern dentistry has evolved to accommodate their fears.

Understanding Where the Fear Comes From

Dental anxiety has many roots, and understanding yours can be the first step toward managing it. For some people, the fear traces back to a painful childhood experience. Dental office technology and anesthesia have improved enormously since the 1980s and 1990s, but a traumatic memory from that era can create a lasting association between dental offices and pain. For others, the anxiety is less about pain and more about loss of control. Lying back in a chair with your mouth open while someone works above you is an inherently vulnerable position.

Some patients tell me their anxiety is primarily about sounds. The high-pitched whine of a dental drill triggers a visceral response that they cannot rationalize away. Others describe fear of judgment, worrying that the dentist will criticize them for the condition of their teeth or for having stayed away so long. I want to address that last one directly: any dentist who shames a patient for seeking care, no matter how long they have been away, is failing at their job. Our role is to help, not to judge.

How Modern Practices Address Anxiety

How do you deal with dental anxiety? The answer today is very different from what it was twenty years ago. Modern dental practices have invested heavily in creating environments and protocols that reduce stress at every touchpoint. It starts before you even sit in the treatment chair. Many offices now feature calming waiting rooms with natural light, comfortable seating, and minimal clinical atmosphere. The days of stark white walls and the smell of disinfectant hitting you at the door are fading.

Communication practices have evolved significantly as well. Many anxious patients tell me that not knowing what is happening is the worst part. So we explain procedures step by step before we begin. We use what I call "tell-show-do," where I describe what I am about to do, show you the instrument I will use, and then proceed only when you give me the go-ahead. We establish hand signals so you can stop the procedure at any moment if you need a break. That sense of control makes an enormous difference for most anxious patients.

Sedation Options Available Today

What do dentists do for patients who are scared? Beyond environmental and communication strategies, we have a spectrum of sedation options that can make treatment comfortable for even the most anxious individuals. Nitrous oxide, sometimes called laughing gas, is the mildest form. You breathe it through a small nose mask, it takes effect within minutes, and it creates a pleasant sense of relaxation while you remain fully awake and responsive. It wears off completely within five minutes of removing the mask, so you can drive yourself home afterward.

Oral sedation involves taking a prescribed medication before your appointment, typically a benzodiazepine that produces significant relaxation. You remain conscious but often have little memory of the procedure afterward. This option works well for patients who need multiple procedures or longer appointments. You will need someone to drive you to and from the office.

For severe anxiety or complex procedures, intravenous sedation provides a deeper level of relaxation while still maintaining consciousness. And for patients who simply cannot tolerate dental treatment while awake, general anesthesia in a hospital or surgical center setting remains an option. The point is that there is a solution for every level of anxiety. No one should suffer through dental care or avoid it because they believe they have to simply endure the fear.

Technology That Has Reduced Pain and Stress

Beyond sedation, advances in technology have made dental procedures genuinely less uncomfortable than they used to be. Topical anesthetics applied before injections mean you often do not feel the needle at all. Computer-controlled anesthetic delivery systems regulate the speed and pressure of the injection, eliminating the sting that older syringes could cause. Laser dentistry can perform certain procedures without drills and sometimes without anesthesia.

Digital impressions have replaced the goopy impression trays that made many patients gag. Smaller, more precise instruments mean less vibration and noise. Quieter electric handpieces are gradually replacing the air-driven drills whose sound triggers so many patients. Each of these advances represents a small improvement, but collectively they have transformed the sensory experience of dental treatment.

Strategies You Can Use on Your Own

While your dental team provides external support, there are strategies you can practice independently. Deep breathing exercises before and during appointments help activate your parasympathetic nervous system and reduce the physical symptoms of anxiety. Many patients find that listening to music or podcasts through headphones during treatment helps distract from sounds and creates a sense of personal space.

Scheduling matters too. If you are a morning person, book the first appointment of the day when you are at your best and have not spent hours worrying. If you function better later, choose an afternoon slot. Avoid scheduling immediately after stressful meetings or events. Some patients benefit from a brief visit to the office before their actual appointment, just to walk in, sit in the waiting room for a few minutes, and leave. This desensitization approach can reduce the novelty anxiety that builds between visits.

Finding a Practice That Understands

Not every dental practice is equally equipped or willing to work with anxious patients. When you call to schedule, mention your anxiety upfront. Notice how the staff responds. Do they seem understanding and accommodating, or dismissive? Ask what specific accommodations they offer. Do they provide sedation options? Will they explain procedures before starting? Do they allow breaks during treatment?

A practice that genuinely cares about anxious patients will have thought about these questions already and will have systems in place. They will not make you feel abnormal for asking. They will welcome the conversation because they know that building trust is the foundation of a successful long-term relationship.

Taking That First Step

If you have been avoiding dental care because of anxiety, I want to acknowledge that making that first phone call takes real courage. Here is what I want you to know: you do not have to go from zero to a full treatment session immediately. Many practices will schedule a consultation appointment where you simply meet the dentist, discuss your concerns, and develop a plan together. Nothing happens to your teeth that day. You are just opening a dialogue.

The patients who finally come back after years away almost always tell me the same thing: the anticipation was far worse than the reality. Modern dentistry, with its emphasis on comfort, communication, and patient autonomy, is genuinely different from what many fearful patients remember or imagine. You deserve dental care that does not traumatize you. It exists, and finding it might be easier than you think.

Read more…

13554687866?profile=RESIZE_584x

I will be honest with you. Choosing a dental office based solely on online reviews is like choosing a restaurant based on the photos alone. You might end up somewhere decent, but you also might miss what actually matters to your experience. As a dentist myself, I have seen patients transfer from highly-rated practices where they felt rushed, confused, or uncomfortable. I have also seen patients thrive in smaller offices with fewer online reviews but exceptional personal care. The star rating tells you something, but it does not tell you everything.

Start with What Your Family Actually Needs

How do I find a good dentist? This is a question nearly every family faces at some point, whether after a move, a change in insurance, or simply growing dissatisfied with their current provider. The first step is to think clearly about what your family actually requires. Do you have young children who need a provider experienced with pediatric behavior management? Do you have a teenager who will need orthodontic referrals? Do you or your spouse have dental anxiety that requires a particularly patient and communicative provider? Does anyone in the family have complex medical conditions that affect dental treatment?

These specifics matter far more than a generic five-star rating. A practice that excels with anxious adults might not have the pediatric setup needed for your four-year-old. A high-volume practice that moves efficiently might feel impersonal to someone who values unhurried conversation with their provider. Knowing your priorities helps you evaluate options through the right lens.

What to Look for When Choosing a Dentist

What should I look for when choosing a dentist? Beyond clinical competence, which I will address separately, look for indicators of how the practice communicates. Call the office and notice how you are treated on the phone. Are they friendly and patient with your questions, or do they seem rushed and transactional? Ask about their approach to treatment planning. Do they explain options and involve patients in decisions, or do they simply tell you what needs to be done?

Notice the physical environment when you visit. Is the office clean and well-maintained? Is the equipment relatively modern? Are the team members welcoming to your children? I always tell friends that the front desk experience is a surprisingly reliable indicator of the overall practice culture. If the team seems happy, engaged, and genuinely helpful, that usually reflects good leadership and a healthy workplace, which translates directly into better patient care.

Credentials and Continuing Education

Every practicing dentist holds a doctorate in dental surgery or dental medicine and has passed national and state board examinations. That baseline ensures competence. But dentistry evolves rapidly, and the best providers invest significantly in continuing education beyond the minimum requirements. Ask whether the dentist pursues advanced training. Many excellent general dentists take hundreds of hours of additional coursework in areas like implants, cosmetic dentistry, or sleep medicine.

Board certification in a specialty, such as orthodontics or periodontics, indicates years of additional residency training in that specific area. If your family needs specialized care, seeking out a board-certified specialist is worthwhile. For general family dentistry, look for a provider who is active in professional organizations and committed to staying current with evidence-based practices.

Insurance, Cost, and Value

Practical considerations matter. Does the practice accept your dental insurance plan? If you do not have insurance, do they offer in-house savings plans or payment options? Cost should be a factor in your decision, but I would encourage you not to let it be the only factor. The least expensive option is not always the best value, and the most expensive option is not automatically superior.

I have seen patients choose a practice because it offered the lowest fees, only to need retreatment within a few years because the work was done too quickly or with substandard materials. I have also seen patients pay premium prices at boutique practices for services that were no different from what they could receive elsewhere at lower cost. The sweet spot is a practice that charges fairly, uses quality materials, takes appropriate time with each patient, and delivers durable results.

Emergency Access and Availability

Something many families do not think about until they need it is emergency access. What happens if your child chips a tooth on a Saturday afternoon? Does the practice have an after-hours call system? Do they see emergencies the same day? Understanding the practice's approach to urgent situations before you face one reduces stress enormously.

Also consider appointment availability for routine care. Some popular practices are booked months in advance, which can make scheduling difficult for busy families. Others have same-week availability that accommodates unpredictable schedules. Neither is inherently better, but one might suit your family's lifestyle more than the other.

The Relationship Factor

Dentistry is a long-term relationship. The best outcomes happen when patients trust their provider, feel comfortable asking questions, and attend appointments consistently over years and decades. That relationship allows the dentist to notice subtle changes, understand your history, and provide personalized recommendations based on knowing you as an individual rather than treating you as a stranger at each visit.

I always encourage families to schedule an initial consultation or new patient exam and treat it as a mutual interview. You are evaluating the dentist just as much as they are evaluating your dental health. Pay attention to how you feel during the appointment. Were your questions answered thoroughly? Did you feel listened to? Did the provider seem genuinely interested in your concerns? Trust your instincts about interpersonal fit. Technical skill is essential, but it is not sufficient if you dread going to your appointments.

Red Flags Worth Noting

While no practice is perfect, certain patterns should give you pause. Be cautious of a provider who diagnoses extensive treatment at your first visit without thorough examination and radiographs. Be wary of pressure to commit to expensive procedures immediately without time to consider your options or seek a second opinion. Question a practice that never seems to involve you in decision-making or that dismisses your concerns without explanation.

Also pay attention to staff turnover. If the office seems to have different people every time you visit, that can indicate management problems that eventually affect patient care. Consistent, experienced team members who know your name and remember your history are a hallmark of a well-run practice.

Getting Recommendations That Matter

While online reviews have their place, personal recommendations from people whose judgment you trust carry more weight. Ask friends, coworkers, or neighbors who they see and what they like about the experience. If you have a medical doctor you trust, ask for their dental referral. Other healthcare providers often have insight into which dentists in the community are particularly skilled and conscientious.

You can also ask a dental specialist for a recommendation. Orthodontists, oral surgeons, and periodontists work with many general dentists in any given area and have direct knowledge of who provides excellent care and communicates well. These peer-to-peer assessments are often the most reliable indicator of clinical quality.

Ultimately, the right dentist for your family is one who combines clinical competence with genuine caring, clear communication, and an environment where every family member feels safe and respected. That combination might not always correlate with the highest star rating online, but it will serve your family well for years to come. Take the time to find that fit. Your oral health, and your family's relationship with dental care, is worth the effort.

Read more…

31148861066?profile=RESIZE_710x

Most people think of a dental exam as a quick look at the teeth followed by a cleaning. You sit in the chair, open wide, hear some poking around, and then the hygienist polishes everything up. Simple, right? In reality, what happens during those few minutes of examination is far more comprehensive than most patients realize. I want to pull back the curtain a bit and walk you through what we are actually looking for, because understanding the process might change how you think about those twice-yearly visits.

The First Thing We Notice

Before I even ask you to open your mouth, I am observing. I notice how your face looks compared to your last visit. Is there asymmetry that was not there before? Any swelling along the jaw or neck? Changes in skin color or texture around the lips? These visual cues can indicate everything from an infected tooth to something more serious that might need referral to a specialist. I had a patient several years ago whose slight facial swelling led to the early detection of a salivary gland issue. She had no idea anything was wrong.

I also look at how you open and close your mouth. Does your jaw deviate to one side? Do you hesitate because of pain? Is there clicking or popping in the temporomandibular joint? These observations happen quickly and naturally as part of the greeting and initial conversation. You probably never notice me doing it.

Inside the Mouth: More Than Just Teeth

What does a dentist look for during a checkup? The answer might surprise you with its breadth. Yes, I examine every tooth surface for signs of decay. But I also evaluate the soft tissues extensively. I look at your tongue, checking for unusual patches, discoloration, or changes in texture. I examine the floor of your mouth, the inside of your cheeks, your palate, and the back of your throat. I palpate the lymph nodes under your jaw and along your neck.

This soft tissue evaluation is essentially an oral cancer screening, and it happens at every single exam whether or not we explicitly announce it. Oral cancer caught early has a survival rate above 80 percent. Caught late, that number drops dramatically. Those few seconds I spend looking at tissue that seems completely unrelated to your teeth could genuinely save your life. I have personally identified three cases of early-stage oral pathology in the past five years that patients had no awareness of.

Evaluating Your Gums

Your gums tell me an enormous amount about your overall oral health and even your general health. I look at their color, which should be a consistent coral pink in most people. Red, swollen, or bleeding gums indicate inflammation, which is the hallmark of gingivitis or its more serious progression, periodontal disease. I check for recession, where the gum has pulled away from the tooth and exposed the root surface. I look for pocketing, which we measure with a small probe that slides gently between the tooth and gum.

Those numbers your hygienist calls out during your appointment are periodontal probing depths. Healthy readings are one to three millimeters. Fours indicate areas that need attention. Fives and above suggest active periodontal disease that requires treatment. These measurements create a map of your gum health that we compare from visit to visit. A site that was a three last year but is a five today tells me something is changing in that area, even if you feel nothing.

Checking Existing Dental Work

Every filling, crown, bridge, and veneer in your mouth has a lifespan. Part of my exam involves evaluating the integrity of existing restorations. I look for margins where a filling meets the tooth, checking whether they are still sealed or whether gaps have formed that could allow bacteria underneath. I check crowns for fractures, looseness, or areas where the cement seal may be breaking down. Old amalgam fillings get examined for cracks or signs that the surrounding tooth structure is weakening.

Catching a failing restoration early means we can replace it while the repair is still straightforward. Missing the problem means the tooth underneath can decay extensively, sometimes to the point where a simple filling replacement becomes a root canal or even an extraction. This is one of the most valuable and least glamorous aspects of routine exams.

Bite and Jaw Assessment

I evaluate how your teeth come together when you bite. Ideally, the forces of chewing should be distributed relatively evenly. When certain teeth bear more force than they should, they can crack, wear excessively, or develop sensitivity. I look for wear facets, which are flat, shiny spots on teeth that indicate grinding or clenching. I check whether your bite has shifted since your last visit, which could indicate a tooth has moved or a restoration is too high.

TMJ evaluation is also part of this process. I palpate the joints in front of your ears, listen for sounds during opening and closing, and note any limitations in range of motion. Many patients live with low-grade jaw discomfort that they have normalized, not realizing it is something we can address.

Radiographs: Seeing What Eyes Cannot

Dental X-rays are not taken at every visit, but when they are due, they reveal a world of information invisible to the naked eye. We can see decay between teeth where two surfaces touch each other. We can evaluate bone levels around tooth roots. We can identify infections at the tips of roots, impacted teeth, cysts, and other pathology within the jawbone. We can see whether wisdom teeth are developing problematically in younger patients or causing silent damage to adjacent teeth.

I have found tumors, extra teeth, and bone loss on routine radiographs in patients who came in feeling perfectly fine. The images provide a baseline that we compare over time, making subtle changes detectable before they become obvious problems.

Why Dental Exams Matter More Than You Think

Why are dental exams important? Because the mouth is connected to the rest of your body in ways that are only becoming clearer with ongoing research. Periodontal disease has been linked to cardiovascular disease, diabetes complications, adverse pregnancy outcomes, and respiratory infections. The bacteria present in an unhealthy mouth do not stay in the mouth; they enter the bloodstream with every meal and every brushing.

Beyond systemic connections, dental exams catch problems when they are small, manageable, and affordable to treat. A tiny cavity caught today is a fifteen-minute filling. That same cavity ignored for two years becomes a root canal and crown costing ten times as much and requiring multiple appointments. The exam itself takes minutes, but those minutes protect you from hours of future treatment.

I think of routine dental exams the same way I think of oil changes for a car. They seem uneventful when everything is running smoothly, and it is tempting to skip them. But the purpose is not to fix what is already broken. The purpose is to catch the small thing before it becomes the big thing. Your dentist is doing far more during those few minutes than counting your teeth and looking for holes. We are conducting a comprehensive evaluation of your oral health, screening for disease, and building a longitudinal record that allows us to detect changes over time. That quiet exam is one of the most valuable preventive tools in all of healthcare.

Read more…

How to Choose Dental Imaging Software That Actually Works in Your Practice

Most platforms look great in a demo. The real test is how they hold up during a packed Tuesday afternoon — and that's what this guide is about. 

Choosing dental imaging software sounds like a straightforward decision. You book a few demos, compare features, and pick the one that looks the best. In reality, it rarely works that way.

Most platforms look good during a demo. The images are clear, the interface is clean, and everything seems fast and easy. But what you don't see in that 30-minute presentation is how the software actually behaves during a busy day in your practice.

How quickly can your team pull up a patient's X-rays between appointments?

What happens when multiple people need access at the same time?

Does it integrate smoothly with your practice management system, or does someone end up manually linking images?

These are the details that don't show up in a feature list, but they are the ones that affect your workflow every single day.

The challenge is that once you choose a dental imaging software, you are not just choosing a tool. You are committing to a system that will shape how your team captures, reviews, and shares images for years. That is why this decision deserves a more practical approach — instead of focusing on what looks good in a demo, it helps to understand what actually matters in day-to-day use.


Start By Assessing Your Current Setup (Not the Software)

Most dentists start by looking at software, but that is actually backwards. Your decision should start with what you already have:

  • Your practice management system
  • Your sensors and imaging hardware
  • Whether you run one location or multiple

The imaging software has to fit into that environment. If it doesn't, you'll end up with workarounds, extra steps, and frustration for your team. A system that works perfectly in one practice may be a poor fit in another simply because the setup is different.


Practice Management System Integration: The Most Important Factor

If there's one thing that matters most, it's integration with your practice management system.

When it works well

  • Images automatically attach to patient charts
  • Claims are easier to manage
  • Your team doesn't waste time

When it doesn't

  • Staff manually link images
  • Files get misplaced
  • Appointments take longer than they should

This is not a small detail. It directly affects efficiency at the front desk and in the operatory. Before choosing anything, confirm that the integration works with your exact PMS setup, not just the name of the system.


Hardware Compatibility and Lock-In

Many dentists don't realize this early enough: your hardware decision often locks you into your software. Some systems only work well with their own sensors or CBCT units. Others are more flexible and support multiple manufacturers.

This matters for two reasons:

  • Cost over time
  • Flexibility when you upgrade equipment

If you choose a locked system, switching later can be expensive and complicated. If flexibility matters to you, look for open compatibility from the start.


Cloud vs. Server-Based Systems

This is one of the biggest structural decisions you'll make, because it affects how your imaging system behaves every day.

Server-Based

  • Runs on a local computer or server
  • Works without internet
  • Requires backups and IT support

Cloud-Based

  • Accessible from anywhere
  • Easier for multi-location practices
  • Depends on a stable internet connection

There's no universal best option. A single-location practice with stable systems may prefer server-based. A growing group practice often benefits from cloud access. The right choice depends on your setup and how you work day to day.


Image Quality and Post-Processing

Most modern systems produce clinically usable images. Where you'll notice differences is in how easy it is to work with those images:

  • Adjusting contrast and brightness
  • Applying filters
  • Comparing images over time

If these tools are slow or awkward, your team will feel it every day. This is something worth testing during a demo using your own types of images.


Workflow and Ease of Use

This is where small issues become big problems over time. Pay attention to:

  • How many clicks it takes to capture and save images
  • How quickly images load
  • How easy it is to find past X-rays

Features like auto-advance, simple templates, and fast search may seem minor, but they save time on every patient. If the software is hard to learn or slows down common tasks, your team will feel it immediately.


Support and Reliability

Things will go wrong at some point. A sensor fails, a system crashes, or an update causes issues. What matters is how quickly those problems get resolved.

Before choosing a platform, look beyond the sales pitch:

  • How easy is it to reach support?
  • How long do users wait for help?
  • What do other dentists say about real experiences?

Good support saves time, stress, and lost production.


AI and Future-Proofing

AI is becoming more common in dental imaging, but it should not drive your entire decision. If it matters to your practice, check:

  • Whether the software supports AI tools
  • Whether it's built in or requires an add-on
  • How it fits into your workflow

If you're not planning to use AI soon, it shouldn't be the deciding factor.


Cost Structure: What Dentists Often Miss

The price you're quoted is rarely the full picture. Make sure you understand:

  • One-time license vs. monthly subscription
  • Support and maintenance fees
  • Costs for updates or upgrades
  • Add-ons like AI or additional users

Some systems seem affordable up front but become expensive over time. Others cost more initially but are more predictable long term.

Choose Based on Workflow, Not Features

The best dental imaging software is not the one with the longest feature list, but the one that fits your practice and works smoothly every day.

If your team can capture images quickly, find them instantly, and use them without friction, the software is doing its job. But if it slows things down, creates extra steps, or causes confusion, those small issues will add up quickly.

Focus on how the system works in real life, not just how it looks in a demo. That's what makes the difference over time.


Read more…

Teeth-loss-After-Braces-1024x683.jpg

One of the most common questions I get from patients over 40 is whether their age will prevent orthodontic treatment from working properly. I understand the concern. We all know that bones change as we age, and it seems logical that moving teeth through bone would become harder or even risky as the years go by. The reality is more nuanced than a simple yes or no, and I think it is important for patients to understand what actually happens at the biological level when we move teeth.

How Teeth Actually Move Through Bone

To understand how age and bone density factor in, you first need to know the basics of tooth movement. Teeth are not embedded directly in bone like nails in concrete. They are suspended in their sockets by a thin ligament called the periodontal ligament, or PDL. When orthodontic force is applied to a tooth, the PDL on one side compresses while the other side stretches. This triggers a biological response: cells called osteoclasts dissolve bone on the compression side, while osteoblasts build new bone on the tension side. The tooth slowly drifts through the bone as this remodeling cycle continues.

This process works at any age. I have moved teeth successfully in patients in their 70s. The biology does not shut off just because you celebrated a certain birthday. However, the rate and efficiency of this remodeling can change with age, and that is where bone density enters the conversation.

Does Age Affect How Braces Work

Does age affect how braces work? Yes, but perhaps not in the way you might expect. The primary difference is speed. Younger patients, particularly teenagers, have bones that are still developing and remodeling actively. Their cellular turnover is high, which means the osteoclast and osteoblast cycle happens quickly. In adults, especially those over 50, this cellular activity slows somewhat. The result is that teeth may move more gradually, and treatment may take a few additional months compared to the same case in a younger patient.

But slower does not mean impossible, and it does not mean dangerous. In fact, moving teeth slowly and carefully is often ideal because it allows the bone to rebuild properly and reduces the risk of root resorption, which is a slight shortening of the tooth roots that can occasionally occur during orthodontic treatment. Gentle, consistent forces applied over an appropriate timeframe work beautifully in adult bone.

Bone Density and What It Means for Your Teeth

Can you move teeth with less bone density? This is the critical question, and the answer requires some context. Bone density varies throughout the mouth and from person to person. Some adults have dense, thick cortical bone that provides robust support for their teeth. Others, particularly postmenopausal women or individuals with certain medical conditions, may have reduced bone density due to systemic factors like osteoporosis.

Here is the distinction that matters: there is a difference between reduced bone density and reduced bone volume. Density refers to how mineralized and compact the bone is. Volume refers to how much bone is actually present around the teeth. Orthodontic treatment can work with reduced density as long as adequate bone volume exists to support the teeth during movement. When both density and volume are compromised, we need to proceed with extra caution and possibly modify our approach.

I recall a patient in her mid-50s who had been told by another provider that she was not a candidate for braces because of her osteoporosis diagnosis. When I evaluated her, I found that while her systemic bone density scores were low, her jaw bone around the teeth was actually quite adequate. She completed treatment successfully over about 26 months with beautiful results and no complications. The lesson here is that a DEXA scan of your hip or spine does not automatically tell us what your jaw bone looks like.

Medical Conditions That Affect Treatment Planning

Several conditions can affect bone quality in the jaw, and any good orthodontist will ask about them during your initial evaluation. Osteoporosis is the most commonly discussed, but it is not the only factor. Long-term use of certain medications, including bisphosphonates prescribed for bone loss, can actually affect how bone remodels. These medications work by slowing osteoclast activity, which is the very process we rely on for tooth movement. If you take bisphosphonates, your orthodontist needs to know so treatment forces and timelines can be adjusted accordingly.

Diabetes, when poorly controlled, can also affect bone healing and increase the risk of periodontal complications during treatment. Smoking reduces blood flow to the gums and bone, impairing the remodeling process. Vitamin D deficiency, which is remarkably common, can reduce calcium absorption and affect bone quality. These are all manageable factors, not automatic disqualifiers. They simply inform how we approach treatment.

What Your Orthodontist Evaluates Before Starting

Before beginning treatment on any adult patient, I take a comprehensive set of records that goes beyond what we might need for a teenager. This includes a full-mouth series of dental radiographs to evaluate bone levels around every tooth, a panoramic radiograph to look at overall jaw bone quality, and sometimes a cone-beam CT scan for three-dimensional assessment. I also evaluate the health of the periodontal ligament and gums through probing measurements and clinical examination.

If I see areas of bone loss from previous periodontal disease, those areas need to be stable and well-maintained before we begin moving teeth. Orthodontics and periodontal disease do not mix well. The good news is that once periodontal disease is treated and controlled, orthodontic movement can actually improve bone support in some cases by repositioning teeth into more favorable positions within the bone.

How We Modify Treatment for Bone Concerns

When I treat a patient with bone density concerns, I make several adjustments. First, I use lighter forces. Heavier forces do not move teeth faster; they can actually damage the PDL and surrounding bone. Lighter forces allow for healthier, more predictable remodeling. Second, I extend the intervals between adjustments to give the bone more time to respond and rebuild. Third, I monitor more closely with periodic radiographs to ensure that bone levels remain stable throughout treatment.

I may also coordinate with the patient's physician or periodontist to ensure that any systemic bone health issues are being appropriately managed during treatment. This team approach gives us the best chance of an excellent outcome.

Protecting Your Results Long-Term

One thing adult patients need to understand is that retention after treatment is particularly important when bone density is a factor. Teeth naturally want to drift back toward their original positions, and this tendency can be more pronounced when bone is less dense. Permanent retainers bonded behind the teeth, combined with removable retainers worn at night, provide the stability needed to maintain results for life.

I also encourage my adult patients to maintain excellent oral hygiene, attend regular periodontal maintenance appointments, and address any systemic health factors that could affect their bone over time. Adequate calcium and vitamin D intake, regular exercise, and avoiding smoking all support the bone that holds your newly straightened teeth in place.

The bottom line is this: age and bone density are factors in orthodontic treatment, but they are rarely barriers. With proper evaluation, appropriate force levels, and careful monitoring, adults of nearly any age can achieve the smile they want safely and predictably. If you have been told your bones are too old for braces, I would encourage you to seek a second opinion from an orthodontist who regularly treats adult patients. You might be pleasantly surprised by what is possible.

Read more…

I remember the look on my patient Sarah's face when she finally sat down in my chair for her consultation. She was 38, successful in her career, and had been thinking about straightening her teeth for over a decade. "I feel like I missed my window," she told me. That sentiment is something I hear almost every week, and I want to tell you the same thing I told her: there is no window that closes.

Why So Many Adults Are Choosing Braces Now

AdobeStock_131022108__1___1600868270_88285.jpg

The landscape of orthodontics has shifted dramatically over the past fifteen years. When I started practicing, the majority of my patients were teenagers. Today, nearly one in three of my patients is over the age of 25. Some are in their 30s, many in their 40s, and I even treat patients in their 50s and 60s. The reasons vary. Some adults had braces as teens but experienced relapse because they stopped wearing their retainers. Others simply never had the opportunity as children due to cost or access.

So is it worth getting braces as an adult? Absolutely. The benefits extend far beyond aesthetics. Properly aligned teeth are easier to clean, which reduces your risk of cavities and gum disease. A corrected bite can alleviate jaw pain, reduce abnormal wear on tooth surfaces, and even improve digestion since well-aligned teeth chew food more effectively. I have seen patients experience fewer headaches, less grinding, and improved confidence that affects everything from job interviews to social interactions.

How Adult Treatment Differs from Teenage Treatment

Are braces different for adults than teenagers? In several important ways, yes. The most significant difference is biological. Teenagers are still growing, and their bones are more malleable. This means teeth tend to move a bit faster in adolescents. Adult bone is denser and more mineralized, so tooth movement can be slightly slower. That said, we are not talking about dramatically longer treatment times. Most adult orthodontic cases that would take 18 months for a teenager might take 20 to 22 months for an adult. The difference is measurable but manageable.

Another difference involves the overall dental landscape. Adults are more likely to have existing dental work such as crowns, bridges, veneers, or even missing teeth. I have to plan around these restorations. Sometimes a crown needs to be temporarily modified to accept a bracket, or the treatment plan needs to account for a space where a tooth was extracted years ago. None of this makes treatment impossible; it simply requires more customized planning.

What Patients Wish They Had Known Earlier

After treating hundreds of adult patients, I have compiled an informal list of things they wish someone had told them before they started. The first is about soreness. Adults sometimes experience slightly more discomfort after adjustments than teenagers do, likely because of the denser bone I mentioned. Over-the-counter pain relief handles it well, and the discomfort typically fades within two or three days of each adjustment.

The second surprise for many adults is the adjustment to speaking. If you choose lingual braces, which attach to the back of the teeth, or even traditional brackets, there can be a brief period where your tongue needs to adapt. Most patients tell me this lasts about a week. It is temporary, and it resolves on its own with normal speech practice.

Third, many adults underestimate how much they will need to change their eating habits. You cannot bite into an apple with brackets on the front of your teeth. Cutting food into smaller pieces becomes second nature quickly, but it catches some people off guard at business lunches or dinner dates in those first few weeks.

The Emotional Side of Adult Orthodontics

Something I do not see discussed enough is the emotional component. Many of my adult patients carry years of self-consciousness about their smiles. Starting treatment brings up feelings they did not expect. Some feel vulnerable. Others feel a sense of relief that they are finally addressing something that has bothered them for decades. I had one patient, a 42-year-old attorney, tell me that the day she got her braces off was more emotional for her than passing the bar exam. That might sound dramatic, but when you have avoided smiling in photos for twenty years, getting your confidence back is genuinely life-changing.

On the flip side, some adults worry about how braces will look in professional settings. This concern has become less relevant as clear aligners and ceramic brackets have become mainstream options. Ceramic brackets blend with the tooth color, and aligners are nearly invisible. Many of my patients report that coworkers do not notice for weeks or even months.

Treatment Options That Work Well for Adults

Clear aligner therapy works beautifully for many adult cases, particularly mild to moderate crowding and spacing issues. For more complex cases involving significant bite correction, traditional brackets may be necessary, but modern brackets are smaller, sleeker, and far less noticeable than the metal hardware many of us remember from the 1990s.

Self-ligating brackets are another option that many adults appreciate. They use a sliding mechanism rather than elastic ties, which can mean fewer adjustment appointments and slightly less friction during treatment. I discuss all available options with every patient so we can find the approach that fits their clinical needs and their lifestyle.

Practical Tips for Adults Considering Treatment

If you are thinking about starting orthodontic treatment, here is what I recommend. First, schedule a consultation even if you are not ready to commit. A good orthodontist will give you a clear picture of what treatment would involve, how long it would take, and what it would cost. You are not obligated to proceed just because you walked through the door.

Second, ask about payment plans. Many practices offer interest-free financing that breaks the cost into monthly payments. Orthodontic treatment is an investment, but it does not have to strain your budget all at once. Third, be honest with yourself about compliance. If you choose aligners, you need to wear them 20 to 22 hours per day. If you know you will forget or get frustrated, brackets that stay on your teeth might actually be a better fit for your personality.

Finally, think about timing in relation to your life. There is no perfect time, and waiting for one is how another decade slips by. But if you have a wedding in three months or a major career transition next week, it might make sense to start after those events rather than during them. The treatment will still be there when you are ready.

The patients who come to me in their 30s and 40s almost universally say the same thing once treatment is complete: they wish they had done it sooner. That is not a sales pitch. It is simply what I observe. If straightening your teeth is something you have been thinking about, know that your age is not a barrier. Your teeth can move at any stage of life, and the smile you have always wanted is still within reach.

Read more…

Not All Orthodontic Problems Are Created Equal

ee71cc68-dc6c-4317-8046-4f44a0e7ec93-invisalign-vs-braces-difference_lQDN7a0zz.webp

Straightening teeth is one thing. Correcting a bite is something else entirely. I make this distinction early with every patient because it fundamentally affects which treatment approach will work best. Cosmetic alignment, making teeth look straight from the front, is something Invisalign handles beautifully in nearly all cases. But bite correction involves changing how your upper and lower jaws relate to each other, how teeth come together when you chew, and how forces distribute across your entire dental arch. That is a more complex engineering challenge.

Can Invisalign fix an overbite? Yes, in many cases it can. But the type of overbite, its severity, and its underlying cause all influence whether aligners alone will do the job or whether traditional braces offer a more predictable path. I want to give you an honest framework from an orthodontist perspective for understanding when Invisalign excels at bite correction and when it has limitations.

Types of Bite Problems

An overbite refers to excessive vertical overlap of the upper front teeth over the lower front teeth. A moderate overbite, where the upper teeth cover fifty to seventy percent of the lower teeth, is quite common and often treatable with Invisalign. The aligners use intrusion mechanics, gradually pushing the front teeth up into the bone, combined with attachments that provide the necessary grip for vertical tooth movement.

An overjet is different from an overbite, though patients often confuse the two. Overjet refers to the horizontal distance between the upper and lower front teeth. When upper teeth protrude significantly forward, that is an overjet problem. Invisalign can address mild to moderate overjet effectively, particularly when the issue is dental rather than skeletal in origin.

Underbites, where the lower teeth sit in front of the upper teeth, are more challenging for clear aligners. Mild dental underbites, caused by tooth positioning rather than jaw growth discrepancy, can sometimes be treated with Invisalign. Skeletal underbites, where the lower jaw itself has grown too far forward relative to the upper jaw, typically require braces, sometimes in combination with jaw surgery.

Crossbites occur when some upper teeth sit inside the lower teeth rather than outside. Posterior crossbites affecting back teeth can be treated with Invisalign if the issue is dental tipping rather than a true skeletal width discrepancy. Anterior crossbites of one or two teeth often respond well to aligner treatment.

Open bites, where the front teeth do not touch when the back teeth are together, are historically one of the most challenging problems for any orthodontic appliance. Interestingly, Invisalign has shown surprising effectiveness for certain types of anterior open bites because the plastic covering the back teeth can act as a bite block, allowing the front teeth to erupt and close the gap. This is an area where aligners sometimes outperform braces.

Where Invisalign Excels

Is Invisalign as effective as braces for bite problems? For certain bite issues, it is equally effective and sometimes even advantageous. Mild to moderate overbites respond well to Invisalign when the treatment plan includes precision-cut attachments and carefully sequenced movements. Class II corrections using elastics, rubber bands that hook from upper to lower aligners, have become increasingly reliable.

Invisalign also works well for bite problems that require intrusion of teeth, meaning pushing teeth deeper into the jawbone. The full coverage of the aligner acts as a platform for intrusive forces that are actually quite difficult to achieve with traditional braces without additional hardware. For patients with deep bites who have worn down their front teeth, Invisalign can open the bite effectively while simultaneously straightening the teeth.

Another area where aligners shine is in treating posterior open bites and uneven bite planes. The material itself acts therapeutically; by covering the biting surfaces, it controls which teeth are in contact and which are free to erupt or intrude.

Where Braces Still Have the Edge

Braces maintain advantages in several specific clinical scenarios. Significant anteroposterior jaw discrepancies, where the upper and lower jaws are substantially misaligned front to back, often require the heavier forces and more precise three-dimensional control that fixed brackets and wires provide. Cases requiring significant vertical movement of back teeth, such as molar uprighting or impacted tooth guidance, are more predictable with braces.

Complex cases requiring extractions for bite correction also tend to favor braces, particularly when large spaces need to be closed. While Invisalign can close extraction spaces, the mechanics of sliding teeth along an arch are more straightforward with a continuous archwire. The control over root positioning during space closure is generally more precise with brackets.

Severe rotations of premolars and canines, situations requiring torque control of root angles, and cases with significant skeletal components are all areas where I am more likely to recommend traditional braces. This is not a criticism of Invisalign. It is simply an honest assessment of where each tool performs best.

The Hybrid Approach

Something I discuss with patients more frequently now is the hybrid treatment approach. This involves using braces for one phase of treatment, typically the heavy mechanical movements and bite correction, and then transitioning to Invisalign for the finishing and detailing phase. Or vice versa: starting with aligners to address alignment and then using short-term fixed appliances to fine-tune the bite.

I had a patient last year with a significant Class II bite and moderate crowding. We used Invisalign with elastics for the first twelve months to address the crowding and begin the bite correction, then placed partial braces on the upper arch for four months to achieve the final bite precision we wanted. The patient was thrilled because she had braces for only a short period, and the overall result was excellent.

Making the Right Decision

The most important factor in choosing between Invisalign and braces for bite correction is an accurate diagnosis. Not all overbites are the same. Not all underbites have the same cause. A thorough evaluation that includes photographs, digital scans, and radiographs allows your orthodontist to determine exactly what type of movement is needed and which tool will accomplish it most efficiently.

I encourage patients to ask their orthodontist specific questions. What type of bite problem do I have? Is it dental or skeletal? What movements are required to correct it? Are those movements within the predictable range for aligners? If there is any doubt, what is the backup plan? A good orthodontist will welcome these questions and give you honest answers rather than defaulting to one approach for every patient.

Both Invisalign and braces are extraordinary tools, and the best orthodontic outcome comes from choosing the right tool for the specific job. Sometimes that is aligners. Sometimes that is braces. Sometimes it is a combination. The goal is always the same: a healthy, functional bite and a smile you love.

Read more…

Why Tray Hygiene Matters More Than You Think

How-Do-You-Clean-Invisalign-Trays.jpg

I have a confession. Early in my career, I did not spend nearly enough time talking to patients about how to clean their Invisalign aligners. I assumed it was obvious. You wear something in your mouth all day, you keep it clean. But after seeing enough patients come in with cloudy, smelly trays and early signs of tooth decay, I realized that tray hygiene deserves its own detailed conversation. What goes on with your aligners directly affects what happens to your teeth underneath.

Your Invisalign trays spend twenty-two hours a day pressed against your teeth and gums. They create a sealed environment where saliva flow is reduced and anything trapped between the tray and your enamel sits there for hours. Clean trays over clean teeth create a healthy environment. Dirty trays over imperfectly cleaned teeth create a breeding ground for bacteria. The stakes are higher than most patients realize.

The Daily Cleaning Routine

How do you clean Invisalign trays? The good news is that it does not require expensive products or complicated steps. Every morning when you remove your trays, rinse them under cool or lukewarm running water. Never use hot water, as it can warp the plastic. Then use a soft-bristled toothbrush, one separate from the brush you use on your teeth, and gently scrub all surfaces of the aligners with clear, uncolored liquid soap or a very mild dish soap. Rinse thoroughly and reinsert.

At night before bed, repeat this process. If you want to do a deeper clean, soak your trays for fifteen to twenty minutes in a denture cleaning solution or in a mixture of equal parts water and white vinegar. Some patients prefer using the branded Invisalign cleaning crystals, which work well but are not strictly necessary. The key is consistency rather than the specific product you use.

Throughout the day, every time you remove your trays to eat, give them a quick rinse under water before setting them in their case. Do not leave them sitting out on a table or wrapped in a tissue. They dry out, bacteria multiply on the surface, and they develop that stale smell that so many patients complain about.

Can Dirty Invisalign Cause Cavities

Can dirty Invisalign cause cavities? Absolutely, and this is something I wish more patients understood before starting treatment. Here is the mechanism. When you eat, food particles and sugars remain on and between your teeth. If you do not brush thoroughly before reinserting your aligners, those particles get sealed against your enamel for hours. The aligner prevents saliva, your mouth's natural cleaning and remineralizing agent, from reaching those surfaces effectively. Bacteria feed on the trapped sugars, produce acid, and that acid sits in direct contact with your enamel without the buffering effect of saliva.

I have seen patients develop multiple cavities during Invisalign treatment, and in almost every case, the issue was inadequate oral hygiene combined with poor tray maintenance. It is preventable. The combination of dirty trays and unbrushed teeth is what creates the problem. Either factor alone is far less dangerous than the two together.

Patients who had perfect dental checkups before Invisalign can develop decay during treatment if they get sloppy with their routine. I emphasize this not to scare anyone but to underline that the hygiene component of aligner treatment is just as important as wearing the trays for the required number of hours.

Signs Your Trays Need Better Care

There are several warning signs that your cleaning routine is not cutting it. If your trays develop a visible cloudiness or white film that does not rinse away, bacteria and mineral deposits have built up. If your aligners smell bad when you remove them in the morning, bacterial colonies have established themselves on the surface. If you notice your trays are turning yellow or have a slightly off color, staining has occurred and cleaning needs to be more thorough.

A patient once brought me her trays and asked why they had turned orange. After some detective work, we realized she was drinking turmeric tea with her aligners in. The staining was dramatic and permanent on that set of trays. While that is an extreme example, even clear water will not remove all buildup if you are not physically brushing the tray surfaces daily.

Products to Avoid

Toothpaste is one of the most commonly misused products with Invisalign trays. Many toothpastes contain abrasive particles designed to polish enamel, and those same particles will scratch the smooth surface of your aligners. Scratched plastic becomes cloudy, harbors more bacteria in the tiny grooves, and becomes more visible on your teeth. Stick to clear liquid soap or products specifically designed for aligners.

Colored or scented mouthwash is another product to avoid for soaking your trays. The dyes can tint the plastic, and some mouthwash formulations contain alcohol that may affect the material over time. If you want to use mouthwash as part of your oral hygiene routine, that is fine, but rinse your trays separately with plain water or soap.

Avoid using boiling water, bleach, or harsh household cleaners. I mention this because I have genuinely had patients try all three. Boiling water instantly deforms the trays. Bleach can degrade the plastic and is not safe to put in your mouth afterward, even with rinsing. General household cleaners contain chemicals never intended for oral contact.

How Often Is Often Enough

At minimum, clean your trays twice daily with soap and a brush: once in the morning and once at night. A deeper soak two to three times per week is ideal. If you are someone who drinks only water throughout the day, has excellent oral hygiene, and never eats with trays in, you might be fine with the twice-daily brush alone. If you occasionally slip up, if you sometimes reinsert trays without brushing first, or if you are prone to dry mouth, more frequent cleaning and soaking becomes important.

Remember that you switch to new trays every one to two weeks, depending on your treatment plan. This built-in refresh cycle means that even if your trays accumulate some buildup toward the end of their wear period, you are starting fresh soon. This does not excuse poor hygiene during that window, but it does provide some reassurance that you are not wearing the same trays for months on end.

Making It Easy on Yourself

The patients who maintain the best tray hygiene are the ones who set up systems that make cleaning effortless. Keep a dedicated aligner brush next to your bathroom sink. Keep a travel cleaning kit in your bag or desk at work. Set a phone reminder if you tend to forget the evening soak. Make it part of your existing routines rather than an additional task you have to remember.

I tell patients to think of their aligners the same way they think of contact lenses. You would not sleep in dirty contacts or put them back in without cleaning them properly. Your aligners deserve the same respect. They are a medical device sitting against your teeth for the vast majority of every day, and treating them with care protects both the trays and, more importantly, your oral health throughout treatment.

Read more…

Eating-and-Drinking-with-Invisalign.jpg

The Official Rules Versus Daily Reality

Every Invisalign patient receives the same basic instructions. Remove your aligners before eating or drinking anything other than water. Brush your teeth before putting them back in. Wear them twenty to twenty-two hours per day. Simple enough on paper. But after treating thousands of patients with clear aligners, I can tell you that the real-world experience of managing food and drink with Invisalign involves far more nuance than those three bullet points suggest.

I want to give you the honest version. The version that accounts for business lunches that run long, morning coffee rituals, date nights, and the general messiness of human life. These are the things my patients ask me about behind closed doors, and I think everyone deserves straight answers before starting treatment.

The Coffee Question

Can you drink coffee with Invisalign? This is probably the single most asked question in my practice, and I understand why. For many people, coffee is non-negotiable. Here is the reality. If you drink hot coffee with your aligners in, two things will happen. First, the heat can slightly warp the plastic over time, potentially affecting the fit and effectiveness of your trays. Second, coffee will stain your aligners, turning them yellow or brown and making them far more visible on your teeth.

My recommendation is straightforward. Remove your aligners for coffee. If you drink one cup in the morning, take the trays out, enjoy your coffee, brush your teeth or at least rinse thoroughly, and put them back in. The whole process adds maybe five minutes to your morning routine. If you are someone who sips coffee for two hours straight, that is a bigger challenge. You might consider switching to drinking your coffee in a more condensed window rather than nursing it all morning.

I have had patients ask about drinking iced coffee through a straw with aligners in. While a straw reduces contact with the trays, it does not eliminate it entirely. The liquid still swishes around in your mouth. It is not the worst thing in the world if it happens occasionally, but making it a daily habit will discolor your aligners and potentially trap sugary or acidic liquid against your teeth.

What You Can Actually Eat

What can you eat with Invisalign? The beautiful answer is: anything. Unlike traditional braces, which come with a long list of forbidden foods like popcorn, caramel, hard candy, and corn on the cob, Invisalign has no food restrictions whatsoever. You simply remove your trays, eat whatever you want, clean up, and put them back.

This is one of the genuine advantages of clear aligners that I emphasize with patients. Want a steak? Go for it. Craving an apple? Bite right in. That bag of sticky caramels your coworker brought back from vacation? Help yourself. The freedom to eat without restriction is a significant quality-of-life benefit compared to traditional braces, and it is one that patients consistently cite as a major reason they chose Invisalign.

The catch, of course, is the time factor. Every eating occasion requires tray removal and reinsertion, and you need to keep your total daily wear time at twenty-two hours. That means you have roughly two hours per day allocated to eating and oral hygiene. For most people, that breaks down to about thirty to forty minutes per meal for three meals. Snacking between meals eats into that allowance quickly.

The Brushing Dilemma

In a perfect world, you would brush and floss after every single meal before reinserting your aligners. In reality, that is not always possible. You are at a restaurant, at a work meeting, at a picnic. I tell patients that the ideal is to brush, but when that is not feasible, rinsing your mouth thoroughly with water is an acceptable temporary solution. Swish vigorously for thirty seconds, rinse your aligners under water, and put them back in. Then brush properly as soon as you can.

What you should never do is eat, skip any rinsing, and immediately put your trays back over food-covered teeth. This traps food debris and sugars against your enamel for hours, which is a recipe for cavities and gum problems. The aligners essentially seal everything against your teeth, creating the perfect environment for bacteria to thrive if food particles are present.

Alcohol and Social Situations

Social drinking presents its own set of considerations. Clear spirits mixed with plain soda or water are the least problematic if you occasionally take a sip with trays in. Red wine, beer, and cocktails with sugar or coloring agents will stain aligners and should always be consumed with trays removed.

I tell patients heading to a social event to plan ahead. Remove your trays, enjoy the event, eat and drink freely, and reinsert when you get home after brushing. If the event runs three or four hours, yes, that exceeds your daily allotment. One evening here and there will not derail your treatment. It is the pattern that matters. If you are removing your trays for extended periods multiple times per week, your treatment timeline will be affected.

A practical tip: bring a small case for your aligners whenever you go out. I cannot count the number of patients who have wrapped their trays in a napkin at a restaurant and accidentally thrown them away. An aligner case in your pocket or purse prevents this surprisingly common and expensive mistake.

Hot Beverages and Temperature

Beyond coffee, patients ask about tea, hot chocolate, and soup. The same principle applies: hot liquids and aligners do not mix well. The thermoplastic material can deform with heat, even if the change is subtle. Room temperature and cold beverages are generally safe with trays in, provided they are just plain water. Anything with sugar, acid, or coloring should still be consumed with trays removed.

Plain sparkling water is a gray area. It is slightly acidic due to carbonation, but in my experience, occasional consumption with trays in does not cause problems. I would not recommend it as your all-day beverage choice, but a glass here and there is unlikely to cause any issues.

Building Sustainable Habits

The patients who manage eating and drinking most successfully with Invisalign are those who establish a routine early and stick with it. They eat structured meals rather than grazing all day. They drink their coffee in one sitting rather than sipping over hours. They carry a small kit with a toothbrush, travel toothpaste, and their aligner case wherever they go.

I also notice that patients do best when they stop thinking of the aligner routine as a burden and start thinking of it as a structure that simplifies their day. You eat at meal times, you take care of your teeth, and the rest of the time your aligners are in and working. Many patients tell me that the routine actually improved their overall dental hygiene habits because they were brushing more frequently and more mindfully than they ever had before.

The key takeaway is this: Invisalign does not restrict what you eat, only when and how you manage the process around it. With a little planning and the right mindset, the adjustment becomes second nature within the first few weeks of treatment.

Read more…

Understanding Dental Crowding

Crowding is one of the most common reasons patients walk through my door. Teeth overlap, twist, and stack up when there simply is not enough space in the jaw for everything to sit neatly in a row. It can range from mild, where one or two teeth are slightly rotated, to severe, where teeth are significantly displaced and layered. For years, traditional braces were considered the only reliable option for anything beyond minor crowding. That has changed substantially.

Can Invisalign fix crowded teeth? Yes, it can, and it does so routinely in my practice. Clear aligners have evolved significantly over the past decade. The technology behind treatment planning, the materials used in the trays, and the ability to use attachments and auxiliary features have made Invisalign a viable option for moderate and even many severe crowding cases. However, the answer comes with important nuances that every patient should understand before choosing a treatment path.

How Aligners Create Space

When teeth are crowded, the fundamental problem is a space deficit. There is not enough room for all teeth to align properly. Invisalign addresses this through several mechanisms, and the treatment plan typically uses a combination of them depending on the severity of your case.

The first and most common approach is called interproximal reduction, or IPR. This involves carefully removing tiny amounts of enamel from between specific teeth to create small increments of space. We are talking about fractions of a millimeter at each site, well within safe limits and completely painless. Across multiple teeth, these small reductions can add up to several millimeters of total space gained. I explain it to patients by comparing it to sanding the edges of puzzle pieces so they fit together without overlapping.

The second mechanism is arch expansion. Aligners can gradually widen the dental arch, particularly in the premolar region, to create additional room. This is done slowly and predictably, and the clear plastic trays are surprisingly effective at producing this type of movement.

The third approach is proclination, which means tipping the front teeth slightly forward to create more room along the arch. This is used judiciously because excessive proclination can look unnatural and may not be stable long term. A good treatment plan balances all three approaches to achieve the best result.

Mild Versus Moderate Versus Severe

For mild crowding, where teeth are off by one to three millimeters, Invisalign is exceptionally effective. These cases are often straightforward, require fewer trays, and finish quickly. Most mild crowding cases can be resolved in four to six months.

Moderate crowding, in the range of four to six millimeters of discrepancy, is where the treatment plan becomes more involved. These cases typically require attachments, which are small tooth-colored bumps bonded to certain teeth that give the aligners something to grip. They also often require IPR at multiple sites and may involve more trays and a longer treatment timeline. I treat moderate crowding with Invisalign regularly, and the results are excellent.

Severe crowding, generally seven millimeters or more, is where the conversation gets more nuanced. Can Invisalign handle it? In many cases, yes, but not all. Severe crowding sometimes involves teeth that are so displaced that an extraction may be necessary to create enough space. Invisalign can absolutely be used in extraction cases, but the treatment is more complex and requires careful planning. Some severe cases with significant vertical displacement of teeth or extreme rotations may still be better served by traditional braces, at least for part of the treatment.

Treatment Duration for Crowding Cases

How long does Invisalign take for crowding? This is one of the most common questions I hear, and the answer depends on severity. For mild crowding, treatment typically ranges from four to eight months. Moderate crowding usually takes twelve to eighteen months. Severe crowding cases can take eighteen to twenty-four months or longer, particularly if extractions are involved or if the treatment plan includes sequential movements that must happen in a specific order.

I always tell patients that these timelines assume good compliance, meaning you are wearing your aligners for twenty to twenty-two hours per day and switching trays on schedule. Patients who wear their trays less consistently will see their treatment timelines extend. I have had patients turn a twelve-month case into an eighteen-month case simply by being inconsistent with wear time.

Attachments and Crowding

If your crowding is anything beyond mild, you will almost certainly have attachments placed on some of your teeth. I want to set realistic expectations here because many patients choose Invisalign specifically for its invisibility, and attachments do add some visibility to the treatment. They are tooth-colored and relatively small, but they are noticeable up close.

Attachments are essential for crowding cases because they provide the leverage and grip points that allow aligners to rotate teeth, extrude them, or move them bodily rather than just tipping them. Without attachments, aligners would simply slide over severely crowded teeth without producing the precise movements needed. Think of them as handles that let the aligner do its work effectively.

When Braces Might Be the Better Choice

I believe in being honest with patients. There are crowding situations where I will recommend braces over Invisalign, or suggest a combination approach. Teeth that are severely rotated, particularly premolars and canines, can be challenging for aligners alone. Cases where teeth are impacted or partially erupted typically need braces. Patients who know they will struggle with compliance, removing and inserting trays consistently, may get better results with fixed braces that work around the clock without patient cooperation.

That said, these situations represent a minority of crowding cases in my practice. The vast majority of patients with crowded teeth, even those with moderate to moderately severe crowding, are excellent candidates for Invisalign. The technology has reached a point where the deciding factor is often patient preference rather than clinical limitation.

What to Expect During Treatment

Treating crowding with aligners is not a perfectly smooth process. Some trays will feel tighter than others, particularly those responsible for the biggest movements. You may notice that certain teeth feel sore for a few days after switching trays, then settle down. This is normal and expected. Your orthodontist will monitor your progress at regular check-in appointments and may make adjustments to the plan if teeth are not tracking as predicted.

Refinement trays are common in crowding cases. After you finish your initial set of aligners, your orthodontist will likely take new scans and order additional trays to fine-tune the result. This is not a failure of the treatment. It is a normal part of the process, especially for more complex crowding. I set this expectation early so patients are not discouraged when they learn they need another round of trays.

The end result, though, is worth the journey. Patients who started with significantly crowded teeth and finish with a beautifully aligned smile consistently tell me it was one of the best decisions they ever made. The fact that they achieved it without metal brackets and wires makes it even more satisfying for them.

Read more…

The Honeymoon Phase Is Real, But So Is the Adjustment

How-long-do-you-wear-your-first-set-of-Invisalign-trays-1296x500.jpg

I hand patients their first set of Invisalign trays with a mix of excitement and gentle warning. On one hand, they are starting a journey toward the smile they have always wanted. On the other hand, I know the next fourteen days will involve a learning curve that no brochure fully prepares you for. I have worn aligners myself, so I speak from both professional and personal experience when I say the first two weeks are their own unique chapter in the Invisalign story.

What is it like to wear Invisalign? The honest answer is that it feels strange at first, then mildly annoying, then completely normal. But that progression takes time, and the first couple of weeks are where most of the strangeness lives. Let me walk you through what actually happens so you know what to expect.

The First Day and Night

When you first snap in your aligners, you will feel pressure. Not sharp pain, but a firm, squeezing sensation across your teeth. It is the feeling of plastic that has been engineered to move your teeth from where they are to where they need to be. Some patients describe it as tightness, others say it feels like their teeth are being hugged. I tell patients to put their first trays in at night, ideally right before bed. This way, the initial hours of adjustment happen while you sleep, and by morning the most intense pressure has already begun to fade.

Does Invisalign hurt the first week? For most patients, I would describe the sensation as discomfort rather than true pain. On a scale of one to ten, most people rate it between a two and a four during the first few days. It is comparable to the soreness you feel after a tough workout, except it is in your mouth. Over-the-counter pain relievers like ibuprofen can take the edge off, and cold water or smoothies feel soothing during those initial days.

Talking with Trays In

Nobody warns you about the lisp. It is temporary, it is minor, but it is real. For the first few days, you may notice a slight change in the way certain sounds come out of your mouth. The S and TH sounds are most commonly affected. I had a patient who was a trial attorney, and she was horrified the first morning she tried to practice her opening statement. By day four, she told me she could not even notice it anymore.

The lisp resolves because your tongue adapts remarkably quickly. Within three to five days, most patients report that their speech sounds completely normal. Reading aloud or talking more during those first days actually speeds up the adaptation. Your tongue simply needs practice navigating around the new plastic in your mouth.

The Eating and Drinking Routine

Here is where the real lifestyle adjustment happens. You need to remove your aligners every time you eat or drink anything other than plain water. That sounds simple until you realize how many times a day you casually sip coffee, snack on something, or grab a handful of trail mix. Suddenly, every bite of food requires a removal, eating, brushing, and reinsertion routine.

During the first week, this routine feels tedious. Patients tell me it takes them fifteen to twenty minutes from start to finish: removing trays, eating, brushing teeth, rinsing trays, and putting them back in. By the second week, most people have it down to five or seven minutes. You get faster at everything, from popping the trays out to brushing efficiently.

Some patients find that they snack less simply because the hassle of removing and reinserting trays is not worth it for a handful of crackers. I have had more than one patient tell me they accidentally lost a few pounds in the first month. That is not the goal, of course, but it is a commonly reported side effect of the routine.

Dry Mouth and Excess Saliva

Your mouth does not know what to make of the aligners at first. Some patients experience dry mouth because they unconsciously breathe through their mouth more, while others produce excess saliva as their body tries to figure out what this foreign object is. Both responses are normal and both settle down within the first week or so.

I recommend keeping a water bottle with you at all times during those early days. Staying hydrated helps with both dry mouth and the general adjustment. Some patients find that their lips feel a bit dry or chapped in the first week as well, so a good lip balm is worth having on hand.

Soreness When Removing Trays

Taking your aligners out will be awkward at first. You have not yet developed the technique, and your fingernails may feel too short for the task. Many patients find that starting from the back molars on one side and working forward is the easiest approach. There are also small plastic tools called aligner removal hooks that can help if you struggle.

Your teeth may feel tender when you first remove the trays, especially during the first few days of a new set. Biting into something immediately after removal can feel odd because your teeth have been under constant gentle pressure. This tenderness is completely temporary and diminishes significantly by the end of the first week.

Sleep and Nighttime Wear

Most patients adjust to sleeping with aligners faster than they expect. The first night might feel unusual. You may notice you clench slightly or wake up aware of the trays. By the third or fourth night, most people forget they are wearing anything at all. If you tend to grind your teeth, the aligners actually serve as a protective barrier, similar to a night guard.

I do hear from occasional patients that they produce more saliva during sleep in the first few nights, which can be mildly annoying. A towel on the pillow helps if this is an issue, and it typically resolves within the first week.

The Emotional Arc

I think it is worth acknowledging the emotional component of those first two weeks. Around day three or four, many patients hit a low point. The novelty has worn off, the routine feels burdensome, their teeth are sore, and they start wondering if they made the right choice. This is entirely normal. I call it the day-four dip, and I tell every patient about it in advance so they recognize it when it happens.

By the end of the second week, something shifts. The routine becomes automatic. The soreness has faded. Your speech is normal. You can remove and insert trays without thinking. You stop noticing the aligners when you look in the mirror. Patients often tell me at their next appointment that week two felt dramatically easier than week one, and that by the time they switched to their second set of trays, the adjustment was minimal.

The first two weeks are the hardest part of Invisalign treatment. Everything after that is repetition with minor discomfort each time you switch to a new tray. If you can get through those fourteen days with patience and a sense of humor, the rest of the journey is genuinely manageable. I promise it gets easier, and I have thousands of patients who would back me up on that.

Read more…

Fear of the dentist is one of the most common problems parents face. A child often associates a dental visit with insecurity, pain, and a loss of control. It's important to understand that timely dental care directly impacts a child's health and overall well-being. If this fear isn't addressed, it can become entrenched and persist into adulthood. In this article, we'll discuss six common reasons for children's dental anxiety and show parents how to manage it.

1. Fear of the unknown

One of the main reasons for children's fear is a lack of understanding of what will happen. Young children are particularly sensitive to new situations, and the dental practice, with its equipment and noises, can be frightening.

To help your child, it's important to explain the treatment process beforehand. Use simple and understandable language and avoid complicated medical terminology. You can also play "dentist" at home and use toys to demonstrate how the dentist examines teeth. Reading children's books or watching cartoons on the subject is also helpful. When a child knows what to expect, their anxiety can decrease significantly.

2. Negative past experiences

If a child has experienced pain or discomfort during a previous visit, they may associate the dentist with unpleasant sensations. Even a single bad experience can trigger persistent anxiety. In such a situation, it's important to take the child's feelings seriously rather than downplaying them. Avoid statements like "It doesn't hurt" or "You're just exaggerating." Instead, discuss what exactly frightened the child and explain that it might be different next time. Choose a compassionate and patient dentist who has experience with children and creates a calm atmosphere.

3. Fear of pain

Even if a child has never had dental treatment before, they may be afraid of pain, especially if they have heard about it from other children or adults. Sometimes parents reinforce this fear by saying, "Don't be afraid, it won't hurt at all." Such words actually make the child think about the possibility of pain.

It's best to speak honestly but sensitively: "It can be a little uncomfortable at times, but the dentist will do everything to make you feel at ease." Modern dentistry offers various pain relief options, and it's important to reassure your child that they will be treated carefully. It's also helpful to discuss with the pediatric dentist beforehand how they explain treatments to children.

4. Feeling of loss of control

During treatment, a child has to sit still, open their mouth, and follow the dentist's instructions. This can trigger anxiety, especially in children who are used to being in control. To reduce stress, make your child feel included. For example, agree on a signal they can give if they feel uncomfortable (for example, raising their hand). Explain that they can take a break at any time. When a child realizes their opinion matters, they feel more secure.

5. Influence of others

Children often adopt the fears of their parents, older siblings, or friends. If someone tells horror stories about dental treatments, a child quickly expects the worst. Parents should therefore be mindful of their choice of words. Avoid sharing your own negative experiences in front of your child. Instead, foster a positive attitude. Explain to your child that the dentist helps keep teeth healthy and beautiful. If possible, accompany your child to checkups and remain calm and composed.

6. Unpleasant environment

Loud noises, bright lights, and strong smells can intensify a child's anxiety. Even adults sometimes feel uncomfortable in a dental practice, and children even more so. Therefore, it is important to choose a practice that is geared towards young patients. A friendly atmosphere, toys, cartoons, and attentive staff contribute to a more relaxed environment. You can also bring your child's favorite toy to give them a sense of security.

The bottom line

Dental anxiety is a normal reaction, especially in childhood. With the right approach, however, it can be significantly reduced or even completely overcome. It's important to support your child, respect their feelings, and gradually create a positive experience at the dentist.

Read more…

That Moment the Brackets Come Off

Braces-bracket-loose-blog-header-e1654188521972-1200x720.jpg

I remember my first patient who asked me about whitening before she even sat down for her debonding appointment. She had been counting down the days until her braces came off, and somewhere along the way she had decided that the very same afternoon would be the day she started whitening. I had to slow her down a bit, and I find myself having that same conversation with patients regularly. The excitement is completely understandable. You have spent months or years investing in a straighter smile, and you want it to look its absolute best. But timing matters more than most people realize when it comes to whitening after orthodontic treatment.

When your braces finally come off, your teeth may look a little uneven in color. Some patients notice lighter spots where the brackets were bonded and slightly darker or more yellow areas around the edges. This is normal. The adhesive that held your brackets in place shielded small patches of enamel from the foods, drinks, and general staining that affected the rest of the tooth surface over the course of treatment. The good news is that this unevenness typically resolves on its own within a few weeks as your teeth re-equilibrate with saliva and normal exposure.

How Long You Should Wait to Whiten

So can you whiten teeth right after braces come off? Technically you can, but I strongly recommend waiting. The general guideline I give my patients is to wait at least two to four weeks after debonding before starting any whitening treatment. Some colleagues recommend waiting as long as six weeks, and honestly, I think erring on the longer side is wise for most people.

Here is why the waiting period matters. When brackets are removed, the enamel surface has just been cleaned of adhesive residue. Your gums may be slightly inflamed from the braces themselves, especially if oral hygiene was challenging during treatment. The tooth surface needs time to remineralize and stabilize. Applying a bleaching agent to freshly exposed, slightly dehydrated enamel can lead to increased sensitivity and uneven whitening results. I have seen patients who jumped in too early end up with splotchy results that took additional treatments to correct.

How long should you wait to whiten teeth after braces? For most patients, I recommend a minimum of two weeks and ideally four to six weeks. During that waiting period, focus on excellent oral hygiene, use a remineralizing toothpaste, and let your enamel recover. Your teeth will actually look better on their own during this time as the color differences from bracket placement begin to even out naturally.

Professional Whitening Options

Once you have waited the appropriate amount of time, you have several options to consider. In-office professional whitening is one of the most popular choices for post-braces patients. These treatments use higher concentration bleaching agents under controlled conditions, and results are visible in a single appointment. I often recommend this route for patients who want dramatic, fast results and who have the budget for it.

Custom tray whitening is another professional option that I frequently suggest. Your orthodontist or dentist can fabricate clear trays that fit your newly straightened teeth precisely. You then use a professional-grade whitening gel at home, typically for thirty minutes to an hour each day over the course of one to two weeks. This approach gives you more control over the process and tends to produce very even results because the trays ensure consistent contact between the gel and your tooth surfaces.

I personally lean toward the custom tray approach for many post-braces patients because it allows for a more gradual whitening process. If sensitivity becomes an issue, you can simply skip a day or reduce the wear time. With in-office treatments, you are committing to the full session in one sitting.

Over-the-Counter Products and What to Watch For

Plenty of patients ask about drugstore whitening strips and similar products. These can work, and they are certainly more affordable than professional options. The active ingredient is usually the same, just at a lower concentration. Whitening strips can be a reasonable choice for patients with mild staining who want a subtle improvement.

However, there are some things to be cautious about. Generic strips and trays are not custom fitted to your teeth, so the whitening gel may not contact all surfaces evenly. This can lead to streaky results, particularly on teeth with any remaining irregularities in alignment. Also, some over-the-counter products contain abrasive ingredients that I would prefer my patients avoid in the weeks immediately following braces removal, when enamel is still recovering.

Whitening toothpastes are the mildest option and are generally safe to use even during the waiting period. They will not produce dramatic results, but they can help maintain brightness and remove surface stains from coffee, tea, or red wine. Just look for one that carries a dental association seal of approval and avoid anything that feels overly gritty.

What to Avoid Entirely

There are a few things I tell every post-braces patient to steer clear of. First, avoid any whitening treatment that involves UV or LED light activation if you are within the first month of having your braces removed. The combination of light and bleaching agents on recently treated enamel can significantly increase sensitivity. Second, do not use charcoal-based whitening products. These are abrasive and can damage enamel that is still in recovery mode. Third, skip any homemade whitening remedies involving lemon juice, baking soda pastes, or hydrogen peroxide rinses mixed at home. The concentrations are unpredictable and the acidity can erode enamel.

I also advise against whitening if you have any active gum inflammation or if your orthodontist noted areas of decalcification, those white spot lesions that sometimes appear around bracket sites. These areas need to remineralize first, and whitening them prematurely can make the spots more noticeable rather than less.

Getting the Best Results

The patients who end up happiest with their post-braces whitening are the ones who approach it patiently and methodically. Wait the recommended time. Choose a method that suits your sensitivity level and budget. Follow the instructions carefully and do not exceed recommended treatment times, thinking that more is better. It is not. Overbleaching leads to translucent, chalky-looking enamel and significant discomfort.

If you had braces as a teenager and are now whitening as an adult, or if significant time has passed since debonding, the waiting period guidelines are less critical. Those apply primarily to the immediate post-treatment window. For anyone whitening months or years after braces, you can generally proceed as any other patient would.

Your orthodontist and general dentist are your best resources for personalized advice. Every patient is different, and factors like enamel thickness, existing sensitivity, and the presence of restorations all influence which approach will give you the safest, most beautiful result. The straight smile you worked so hard for deserves the right finishing touch, and a little patience at the end will pay off with a whiter, healthier result that lasts.

Read more…

Sensodyne-Sensitive-Teeth_after-whitening.jpg?auto=format

You just whitened your teeth and they look great. But now you are wincing every time you drink cold water or breathe in through your mouth on a chilly day. That sharp, zingy sensation is one of the most common side effects of teeth whitening, and while it is not dangerous, it can be genuinely unpleasant. I want to explain exactly why it happens, how long you can expect it to last, and what you can do to minimize the discomfort.

I see this in my practice regularly. Patients are thrilled with their whitening results but caught off guard by the sensitivity that follows. Understanding the mechanism behind it helps take away some of the worry.

What Causes the Sensitivity

Why do teeth hurt after whitening? The peroxide used in whitening products does not just sit on the surface of your enamel. It penetrates through the enamel layer and into the dentin underneath, which is the layer that contains microscopic tubes leading toward the nerve of the tooth. When peroxide reaches those tubules, it causes temporary inflammation and fluid movement within them. Your nerve interprets this as sensitivity or pain, particularly in response to temperature changes, cold air, or sweet foods.

This process is called transient pulpal inflammation, and despite how it sounds, it is not harmful to your teeth. The inflammation is temporary and resolves on its own as the tooth rehydrates and the peroxide byproducts dissipate. Think of it like how your skin might feel irritated after a strong exfoliating treatment; the underlying tissue is fine, but it needs a brief recovery period.

Higher concentrations of peroxide cause more sensitivity for most people. This is why in-office whitening, which uses the strongest formulations, tends to produce more noticeable sensitivity than over-the-counter strips with lower concentrations. Duration of exposure matters as well. Leaving whitening gel on longer than recommended increases the likelihood and intensity of sensitivity.

How Long It Typically Lasts

How long does sensitivity last after teeth whitening? For the vast majority of patients, sensitivity peaks within the first twenty-four to forty-eight hours after treatment and resolves completely within one to three days. Some patients experience it for up to a week, but this is less common and usually associated with higher-concentration treatments or pre-existing sensitivity issues.

I tell patients to plan for two to three days of noticeable sensitivity after professional whitening. For over-the-counter strips used over multiple days, sensitivity may come and go throughout the treatment period but should resolve within a few days of completing the course.

If sensitivity persists beyond ten days, or if it is severe enough that you cannot eat or drink normally, contact your dentist. Prolonged sensitivity after whitening can occasionally indicate an underlying issue that was not apparent before treatment, such as a small crack or early cavity that the peroxide penetrated.

Strategies That Actually Help

There are several evidence-based approaches to managing post-whitening sensitivity, and they range from products you probably already own to techniques you can apply during and after treatment.

Desensitizing toothpaste containing potassium nitrate is your best friend during this period. Potassium nitrate works by calming the nerve endings inside dentin tubules, reducing their ability to transmit pain signals. For best results, start using desensitizing toothpaste one to two weeks before your whitening treatment. This pre-treatment builds up protection in advance and significantly reduces the severity of post-whitening sensitivity.

You can also apply desensitizing toothpaste directly to sensitive teeth and leave it on for a few minutes before rinsing. Some patients apply a thin layer before bed and let it work overnight. This concentrated contact provides extra relief during the peak sensitivity window.

Avoid very hot and very cold foods and beverages for the first forty-eight hours after whitening. Room temperature water, lukewarm coffee, and avoiding ice cream for a couple of days makes a meaningful difference. The sensitivity is primarily triggered by temperature extremes, so moderating what you expose your teeth to during the recovery period reduces discomfort significantly.

Avoid acidic foods and drinks for the first day or two as well. Citrus, tomato sauce, soda, wine, and vinegar-based dressings can exacerbate sensitivity in freshly whitened teeth because the enamel is temporarily more porous after peroxide exposure.

What Your Dentist Can Do

If you are whitening professionally, your dentist has additional tools to manage sensitivity. Many offices apply a fluoride varnish or desensitizing gel immediately after in-office whitening treatment. These products seal the dentin tubules and provide a protective layer that reduces sensitivity onset.

For patients with custom take-home trays, your dentist may recommend alternating whitening sessions with desensitizing gel sessions. One night you wear the whitening gel, the next night you wear a desensitizing product in the same trays. This approach slows the whitening timeline slightly but makes the process far more comfortable.

If you have a history of sensitive teeth in general, not just from whitening, discuss this with your dentist before treatment. They may recommend a lower-concentration product, shorter application times, or a more gradual approach that produces results with less discomfort. There is almost always a way to whiten successfully while managing sensitivity; it just requires adjusting the protocol to your individual tolerance.

Preventing Sensitivity in Future Whitening Sessions

If you plan to maintain your whitening results over time with periodic touch-ups, knowing your sensitivity pattern helps you prepare. The two-week desensitizing toothpaste pre-treatment I mentioned is the single most effective preventive strategy. Building it into your routine before each whitening session dramatically reduces what you experience afterward.

Spacing touch-up treatments appropriately also matters. Whitening too frequently does not produce proportionally better results, but it does increase sensitivity risk. Most patients maintain excellent results with professional touch-ups every six to twelve months or brief strip applications every few months. More frequent than that is unnecessary and increases your chances of discomfort.

Maintaining good enamel health between whitening sessions supports comfort as well. Using fluoride toothpaste daily, avoiding excessive acidic food and beverage consumption, and addressing any cavities or areas of enamel erosion promptly all contribute to teeth that respond to whitening with minimal sensitivity.

The bottom line is this: sensitivity after whitening is normal, temporary, and manageable. It does not mean something went wrong. It simply means the whitening products did their job penetrating your enamel to break apart stains, and your teeth need a brief period to settle back to their baseline. With the right preparation and a few days of gentle care, the discomfort passes and you are left with a brighter, healthier-looking smile.

Read more…

WhatsApp-Image-2025-02-10-at-09.46.25_b601c61e.jpg

Teeth whitening is one of those topics where marketing has thoroughly outpaced education. You see advertisements promising dramatic transformations from products that cost fifteen dollars at the drugstore, and you wonder whether professional teeth whitening, at a significantly higher price point, is really worth it. It is a fair question, and it deserves an honest answer rather than a sales pitch.

I want to break down what actually differs between professional whitening and store-bought strips, explain when each option makes sense, and help you make a decision based on your specific situation rather than advertising claims.

How Whitening Works at a Basic Level

All teeth whitening uses some form of peroxide to bleach stains from tooth enamel. Hydrogen peroxide and carbamide peroxide are the two most common active ingredients, and they work by penetrating the enamel surface and breaking apart the molecular bonds of stain compounds through oxidation. The concentration of peroxide, the duration of contact, and the method of delivery are what differentiate one whitening approach from another.

This is important to understand because it means all whitening products operate on the same fundamental principle. The question is not whether the chemistry works. It does. The question is how effectively and safely a given product delivers that chemistry to your teeth.

What Professional Whitening Offers

Is professional teeth whitening worth it? For many patients, yes. Here is why. In-office whitening uses peroxide concentrations significantly higher than anything available over the counter, typically ranging from twenty-five to forty percent hydrogen peroxide compared to the three to ten percent found in retail products. This higher concentration produces faster, more dramatic results, often in a single appointment lasting sixty to ninety minutes.

Beyond concentration, professional whitening involves customized application. Your dentist or hygienist isolates the gum tissue with a protective barrier before applying the whitening gel, which prevents the high-concentration peroxide from irritating soft tissue. The gel is applied evenly across all visible surfaces, ensuring consistent color change without the patchiness that can occur with strips that do not conform perfectly to tooth contours.

Custom take-home trays from your dentist represent a middle ground. These are fabricated from impressions of your teeth, so they fit precisely and hold whitening gel in uniform contact with every surface. The peroxide concentration is lower than in-office treatment but higher than retail strips, typically ten to twenty percent carbamide peroxide. Treatment involves wearing the trays for a prescribed period over one to two weeks.

The other major advantage of professional whitening is supervision. Your dentist evaluates your teeth before treatment to identify any issues that should be addressed first, such as cavities, cracked teeth, or gum recession that might cause problems during whitening. They can also predict how your teeth will respond based on the type and source of your staining.

What Store-Bought Strips Do Well

Over-the-counter whitening strips are not scams. They contain real peroxide and they do lighten teeth for most users. The concentrations are lower and the contact time is longer (daily use over two to three weeks), but they produce noticeable improvement for many people, particularly those with mild to moderate surface staining from coffee, tea, or wine.

The major advantages of strips are cost and convenience. A box of whitening strips costs a fraction of professional treatment, requires no dental appointment, and can be used on your own schedule at home. For someone with generally healthy teeth, mild staining, and a limited budget, strips represent a reasonable starting point.

Modern strips have improved significantly from early versions. Many now use a hydrogen peroxide concentration around ten percent, and the adhesive technology conforms better to tooth surfaces than it did a decade ago. Results are not as dramatic as professional treatment, but they are real.

The Key Differences That Matter

What is the difference between professional and store-bought whitening? It comes down to several factors that may or may not matter depending on your situation.

Speed and degree of change is the most obvious difference. Professional treatment achieves in one or two sessions what strips take weeks to approximate, and the final result is typically several shades lighter with professional care. If you need significant whitening for an upcoming event or want maximum brightness, professional treatment delivers more reliably.

Uniformity of results is another important distinction. Custom trays and professionally applied gel reach every surface of every tooth evenly. Strips can leave the spaces between teeth, the gum line margins, and the edges of teeth less thoroughly whitened, creating subtle unevenness that bothers some people.

Safety and screening matter as well. If you have untreated cavities, worn enamel, exposed root surfaces, or certain types of dental restorations, whitening without professional guidance can cause problems ranging from intense sensitivity to actual damage. A dental exam before whitening catches these issues. Using strips without that screening means accepting the risk of whitening teeth that are not ready for it.

Longevity of results tends to favor professional treatment as well. The deeper penetration of higher-concentration products often produces results that last longer before requiring touch-up treatments, though individual habits like coffee consumption and smoking status affect duration regardless of the method used.

When Strips Make Sense

If your teeth are healthy, your staining is mild, you have had a recent dental checkup with no noted concerns, and you want modest improvement on a budget, over-the-counter strips are a reasonable choice. They are also appropriate for maintenance between professional treatments, extending the life of a professional whitening result.

I recommend that patients using strips still follow the product directions precisely. More is not better with peroxide products. Overuse or leaving strips on longer than directed increases sensitivity risk without proportionally improving results.

When Professional Treatment Is the Better Call

If your staining is moderate to severe, if you want dramatic results quickly, if you have dental concerns that need evaluation first, or if you have tried strips and found them ineffective, professional whitening is likely the better investment. It is also the better choice for people with dental restorations on visible teeth, since your dentist can advise you on how whitening will interact with crowns, veneers, or bonding.

Ultimately, both options work. The right choice depends on your specific teeth, your expectations, your timeline, and your budget. A conversation with your dentist can help you navigate those variables honestly, without pressure. The goal is a smile you feel good about, achieved safely, regardless of which path gets you there.

Read more…

How+to+Help+Your+Kids+Brush+Better+with+Braces-640w.jpg

Once the braces are on, the real work begins. Not in the orthodontist's chair, but at home, every single day. As a parent, you play a critical role in making sure your child's treatment stays on track. But here is what I have learned after years of working with families: the parents who succeed are the ones who coach rather than police. There is a meaningful difference between nagging your kid about brushing and equipping them with tools and routines that make good habits natural.

This guide is the practical playbook I wish I could hand every parent on the day their child gets braces. It covers the daily essentials, common problems, and strategies that actually work for real families with busy schedules.

The Daily Brushing Routine

How do kids brush their teeth with braces? The technique matters more than most families realize. Brackets create dozens of tiny ledges where food particles and plaque accumulate, and a quick once-over with a toothbrush leaves most of that buildup in place. The key is angle and attention.

Teach your child to brush at a forty-five degree angle, directing bristles both above and below each bracket. The area between the bracket and the gumline is where most problems develop, so spending extra time there is essential. Then angle downward to clean below each bracket toward the biting edge of the tooth. Each tooth needs individual attention on both the front and back surfaces.

A soft-bristled toothbrush works best. Electric toothbrushes with small round heads are excellent for kids with braces because the rotating motion cleans around brackets more effectively than manual brushing for most children. If your child uses a manual brush, make sure they are spending at least three minutes per session, which is longer than the two minutes typically recommended for patients without braces.

Brushing should happen after every meal, not just morning and night. I know that sounds demanding, especially for school days. A travel toothbrush in their backpack makes lunchtime brushing possible. Even a quick rinse with water after eating is better than nothing when a full brushing session is not feasible.

Flossing With Braces

Flossing is harder with braces, which is exactly why it matters more. The wire connecting brackets prevents regular floss from sliding between teeth the normal way. Your child will need either a floss threader, which feeds floss underneath the wire, or an orthodontic flosser designed specifically for braces. Water flossers are another excellent option that many kids find easier and faster than traditional floss.

I recommend flossing once a day, ideally before bed. It does not need to happen after every meal the way brushing should. But that once-daily session is non-negotiable for preventing cavities between teeth and keeping gums healthy throughout treatment.

For younger children or those with limited dexterity, a water flosser can be a game-changer. The pulsing stream of water dislodges food and reduces plaque in areas that are nearly impossible to reach with string floss alone. It is not a complete replacement for traditional flossing, but it is far better than no interproximal cleaning at all.

When Something Breaks

What happens if my child breaks a bracket? First, do not panic. Broken brackets are one of the most common occurrences in orthodontic treatment, and they are almost never an emergency. The bracket may slide along the wire or hang loose, and while it can be annoying, it is not usually painful or dangerous.

Call your orthodontist's office during business hours to schedule a repair. If the broken bracket is causing irritation, orthodontic wax pressed over it will provide immediate relief. If a wire is poking out and causing discomfort, you can use a clean pencil eraser to gently push the wire flat against the teeth, or cover the end with wax until your repair appointment.

The situations that do require prompt attention include a wire that has come completely out of the last bracket and is poking into the cheek or gum, swelling or signs of infection around a bracket site, or significant pain that does not respond to over-the-counter medication. These are uncommon, but knowing the difference between a minor annoyance and something that needs same-day attention gives parents peace of mind.

I tell families that one or two broken brackets over the course of treatment is normal. More than that, and we should talk about whether certain food habits or activities are contributing to the problem.

Making Habits Stick

The biggest challenge for most families is not knowing what to do. It is doing it consistently for months or years. Here are strategies that I have seen work in real households.

Routine anchoring is powerful. Attach brushing to something your child already does without thinking. If they always shower before bed, brushing happens immediately after the shower. If they eat breakfast at the same time each morning, brushing follows within five minutes. Connecting new habits to established ones dramatically improves consistency.

Visible supplies matter more than you might think. A dedicated caddy on the bathroom counter with their orthodontic toothbrush, floss threaders, wax, and mouthwash serves as a visual cue. When everything is out and organized rather than buried in a drawer, the barrier to compliance drops significantly.

For younger children, a simple chart or sticker system can provide motivation during the first few months until the habit becomes automatic. For teenagers, I find that showing them photos of what happens when braces hygiene is neglected, white spots and decalcification marks, tends to be more motivating than any reward system. Teens care about how their teeth will look after braces come off, and that vanity can be channeled productively.

Diet Reminders Without the Power Struggle

Food rules with braces are a common source of parent-child conflict. My advice is to set clear expectations once, stock your home with braces-friendly options, and avoid turning every snack choice into a confrontation.

Keep cut fruit, soft granola bars, yogurt, string cheese, and other easy options visible and accessible. If the convenient choices in your kitchen are all braces-safe, your child will naturally reach for them most of the time. You cannot control what they eat at a friend's house or at school, but you can control what is available at home.

When they do eat something questionable and nothing breaks, resist the urge to lecture. A calm reminder is fine. A repeated lecture creates resentment and makes your child less likely to tell you when something does go wrong. Trust me on this one. I have seen the pattern many times.

Keeping Appointments on Track

Regular adjustment appointments, typically every four to eight weeks, are essential for treatment progress. Missing or repeatedly rescheduling appointments extends treatment time, sometimes significantly. Build these appointments into your family calendar as non-negotiable commitments, similar to how you would treat a recurring medical appointment.

Many orthodontists offer after-school or early morning slots specifically for student patients. If scheduling is a challenge, ask about available times that minimize school absences. Some offices also provide reminder systems via text or email that help busy families stay organized.

Your child's orthodontist is your partner in this process. If something is not working, whether that is compliance with rubber bands, frustration with hygiene, or concerns about treatment progress, bring it up at appointments. We would rather hear about problems early than discover them months later when they have become harder to fix. Open communication between parents, patients, and the orthodontic team is what produces the best outcomes.

Read more…